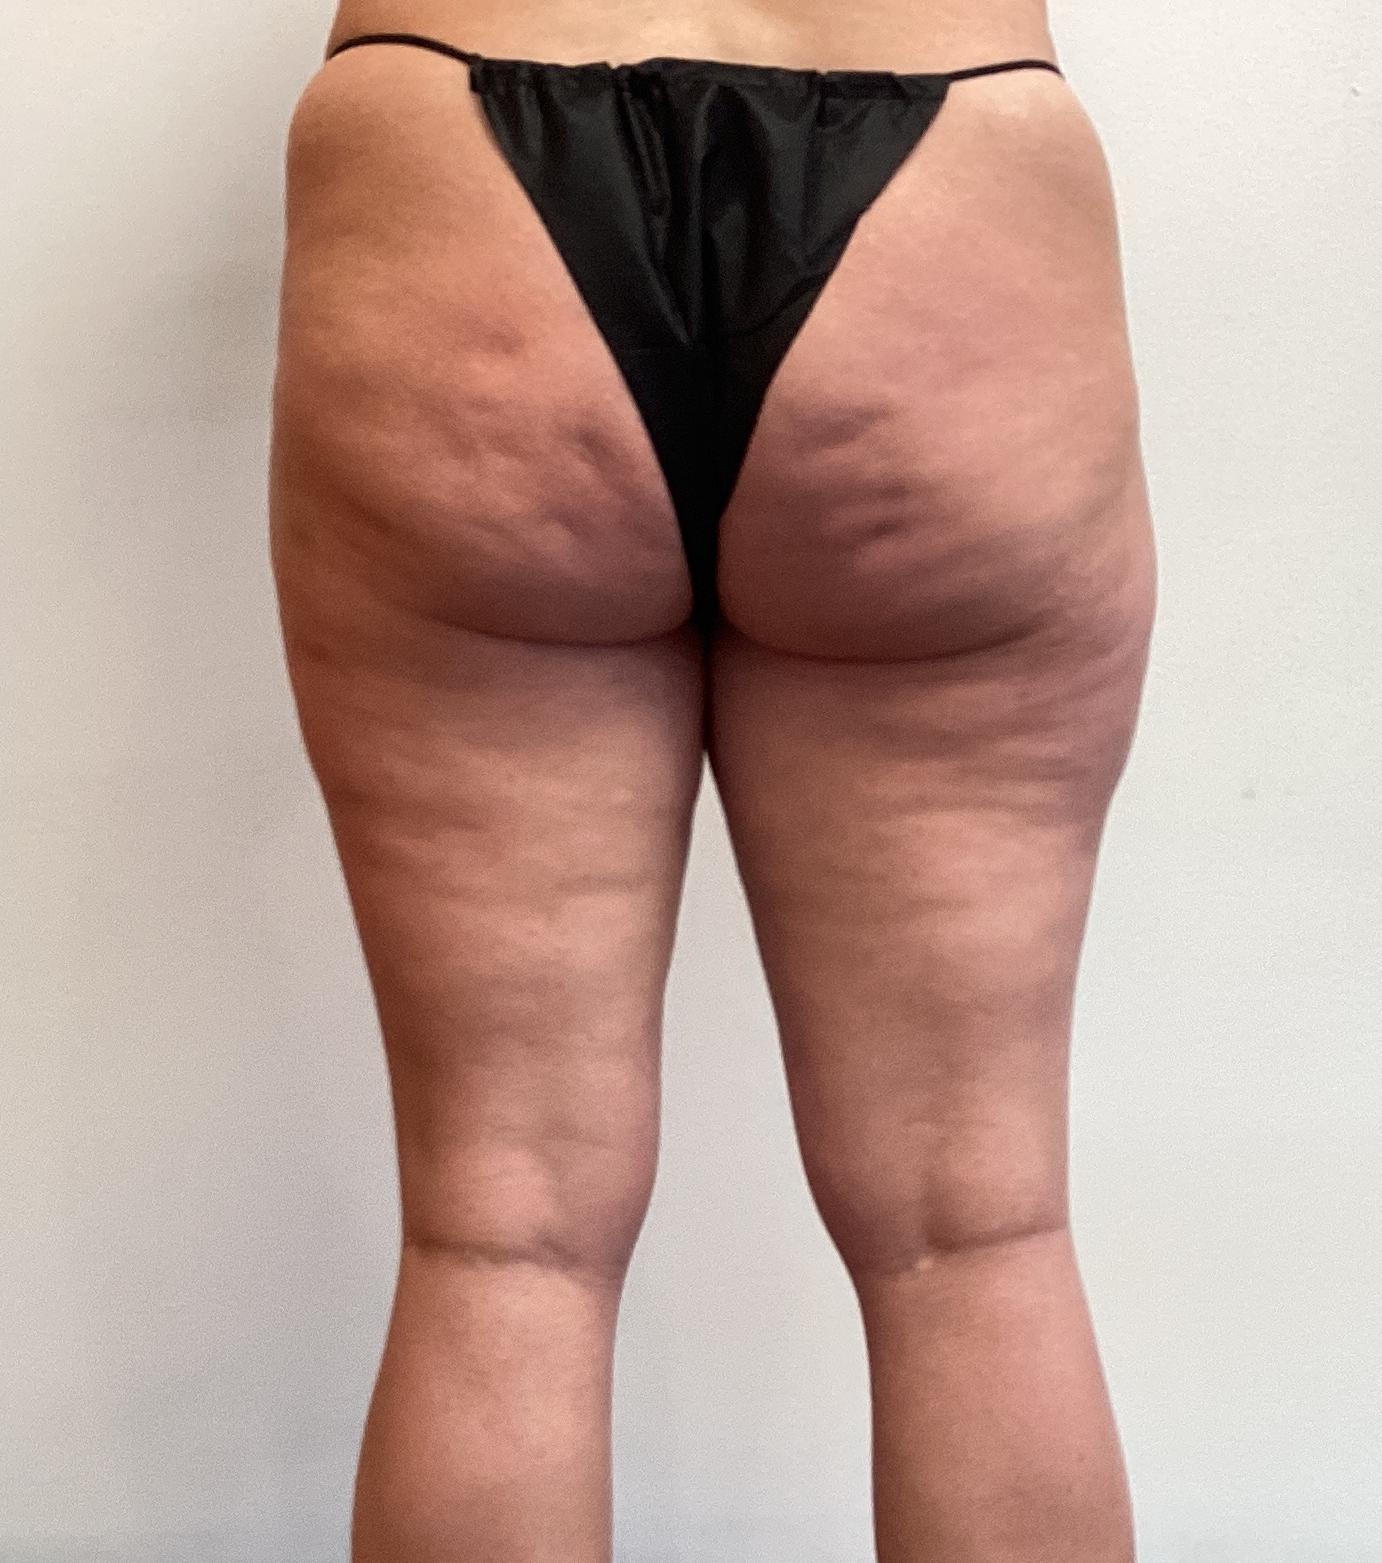
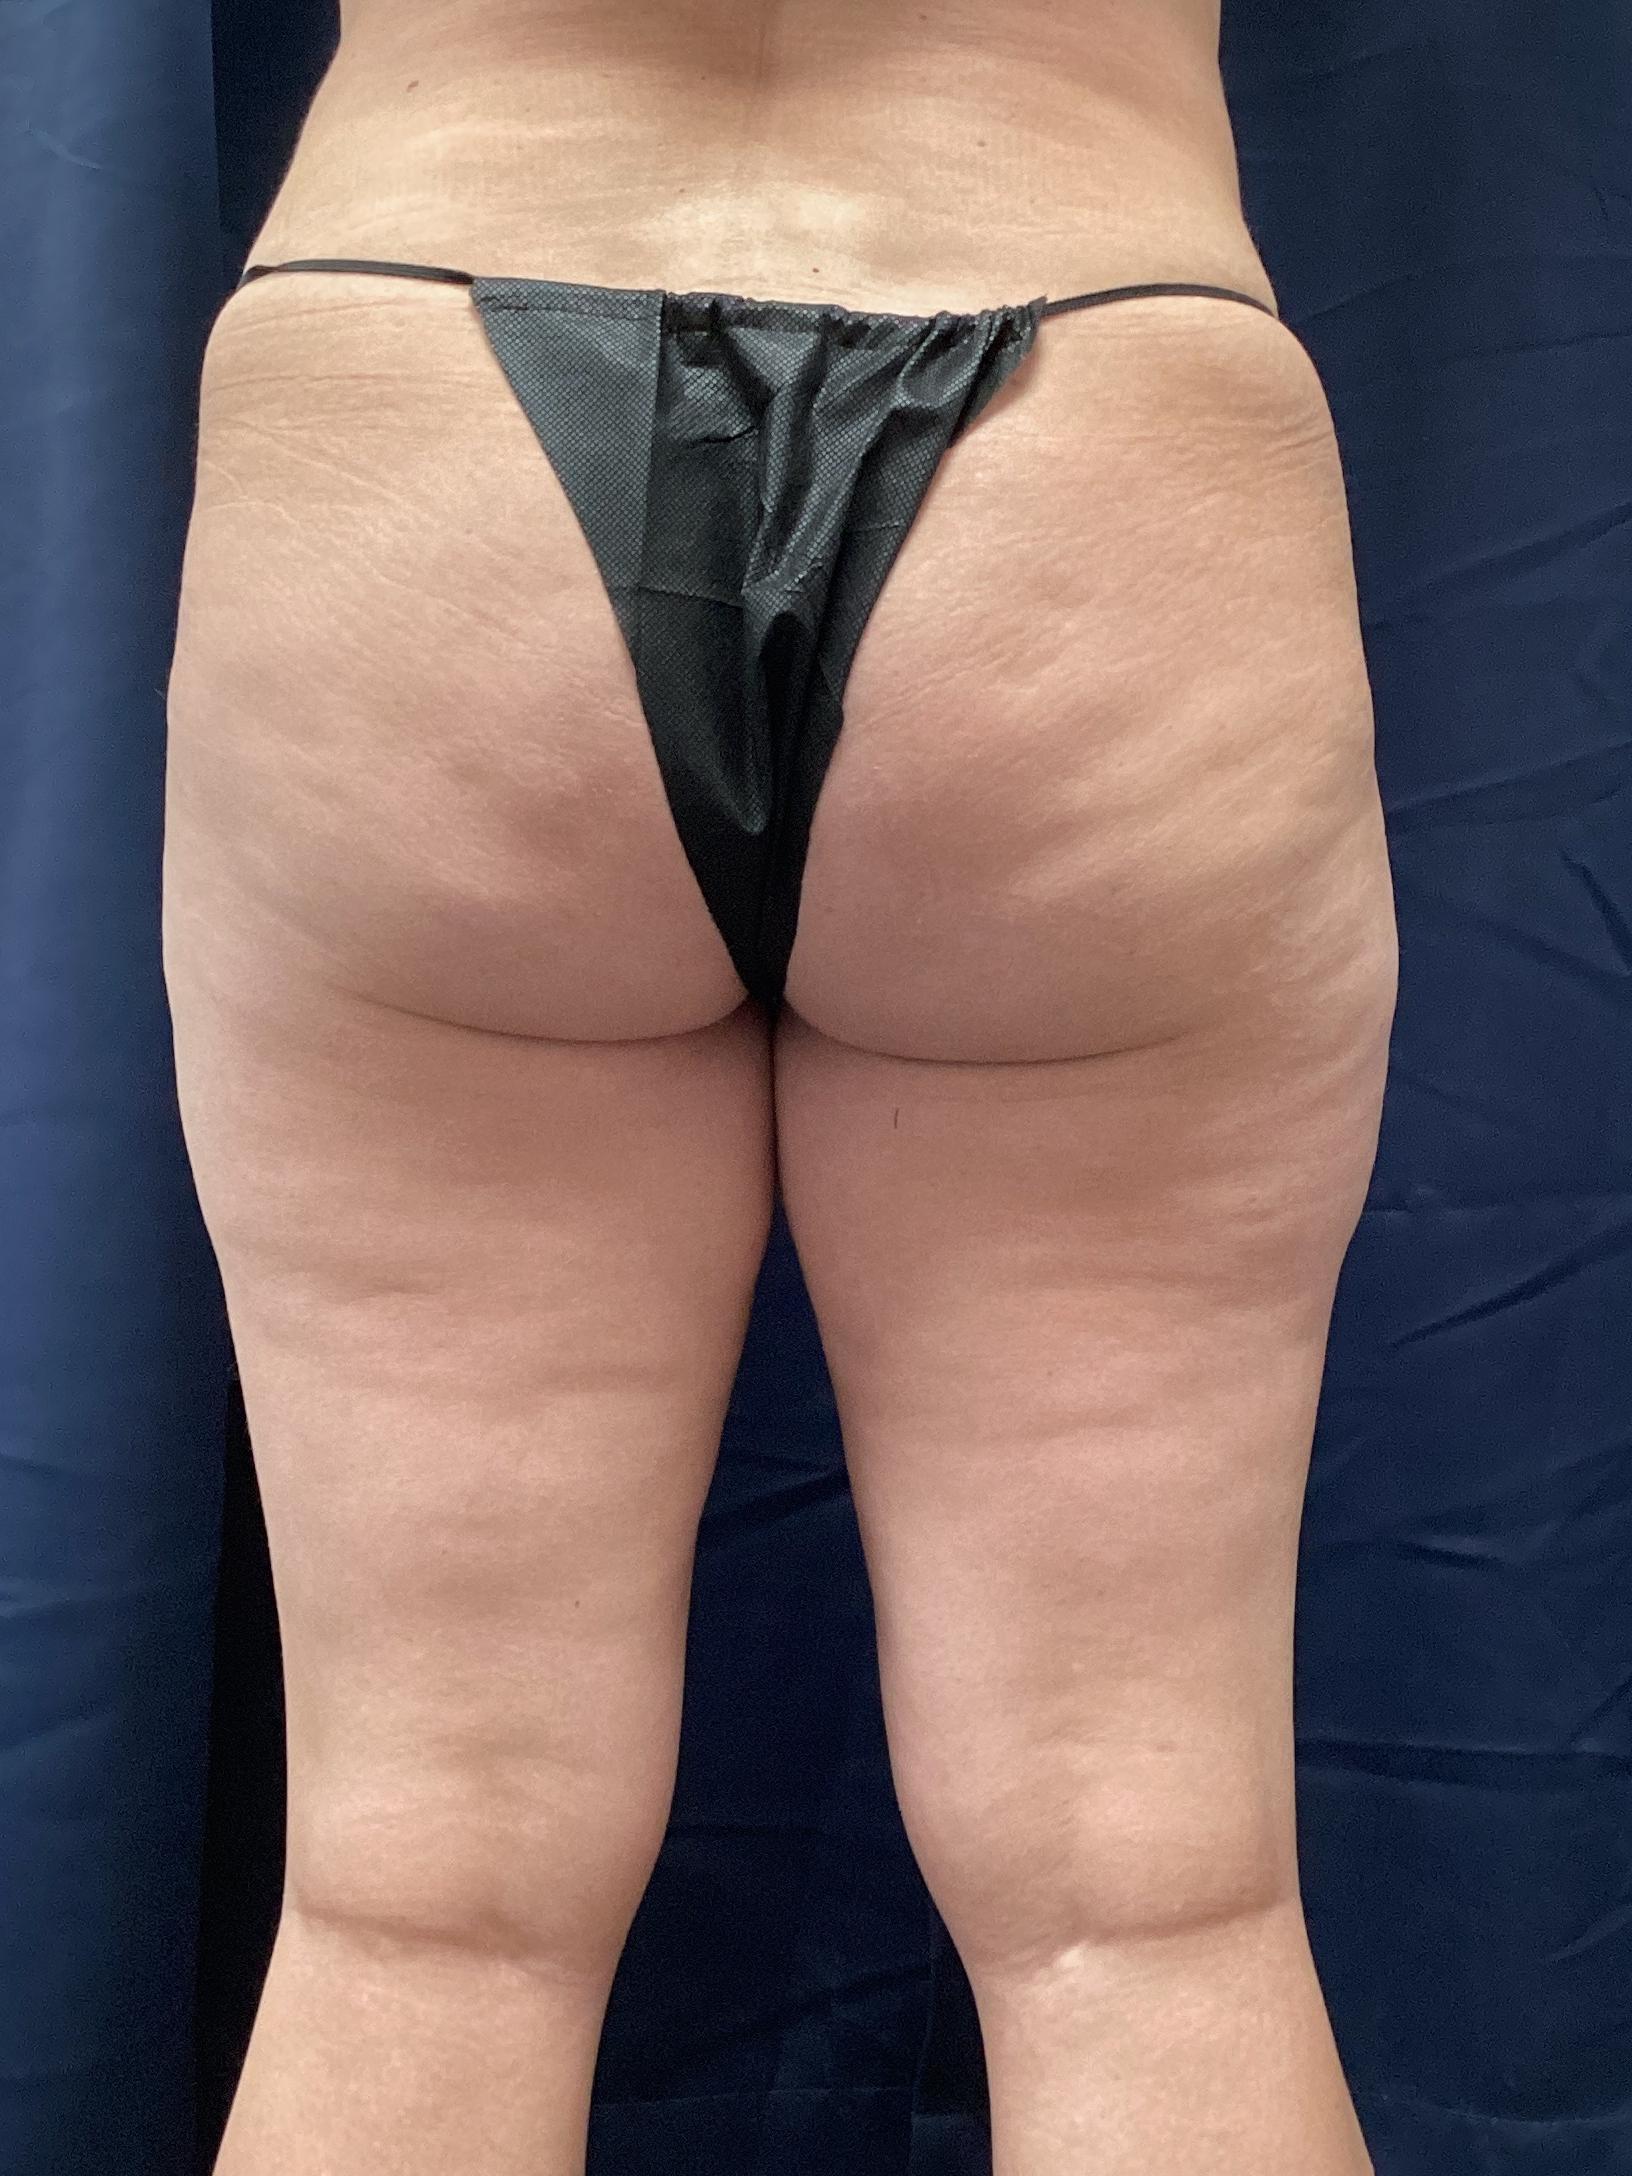
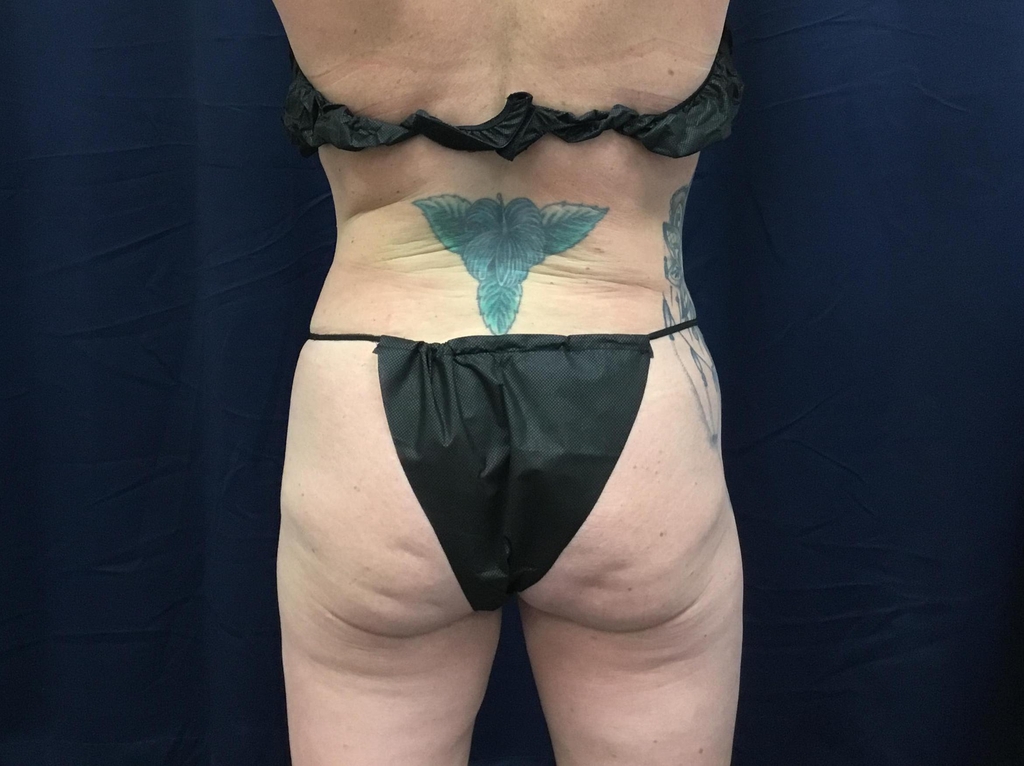
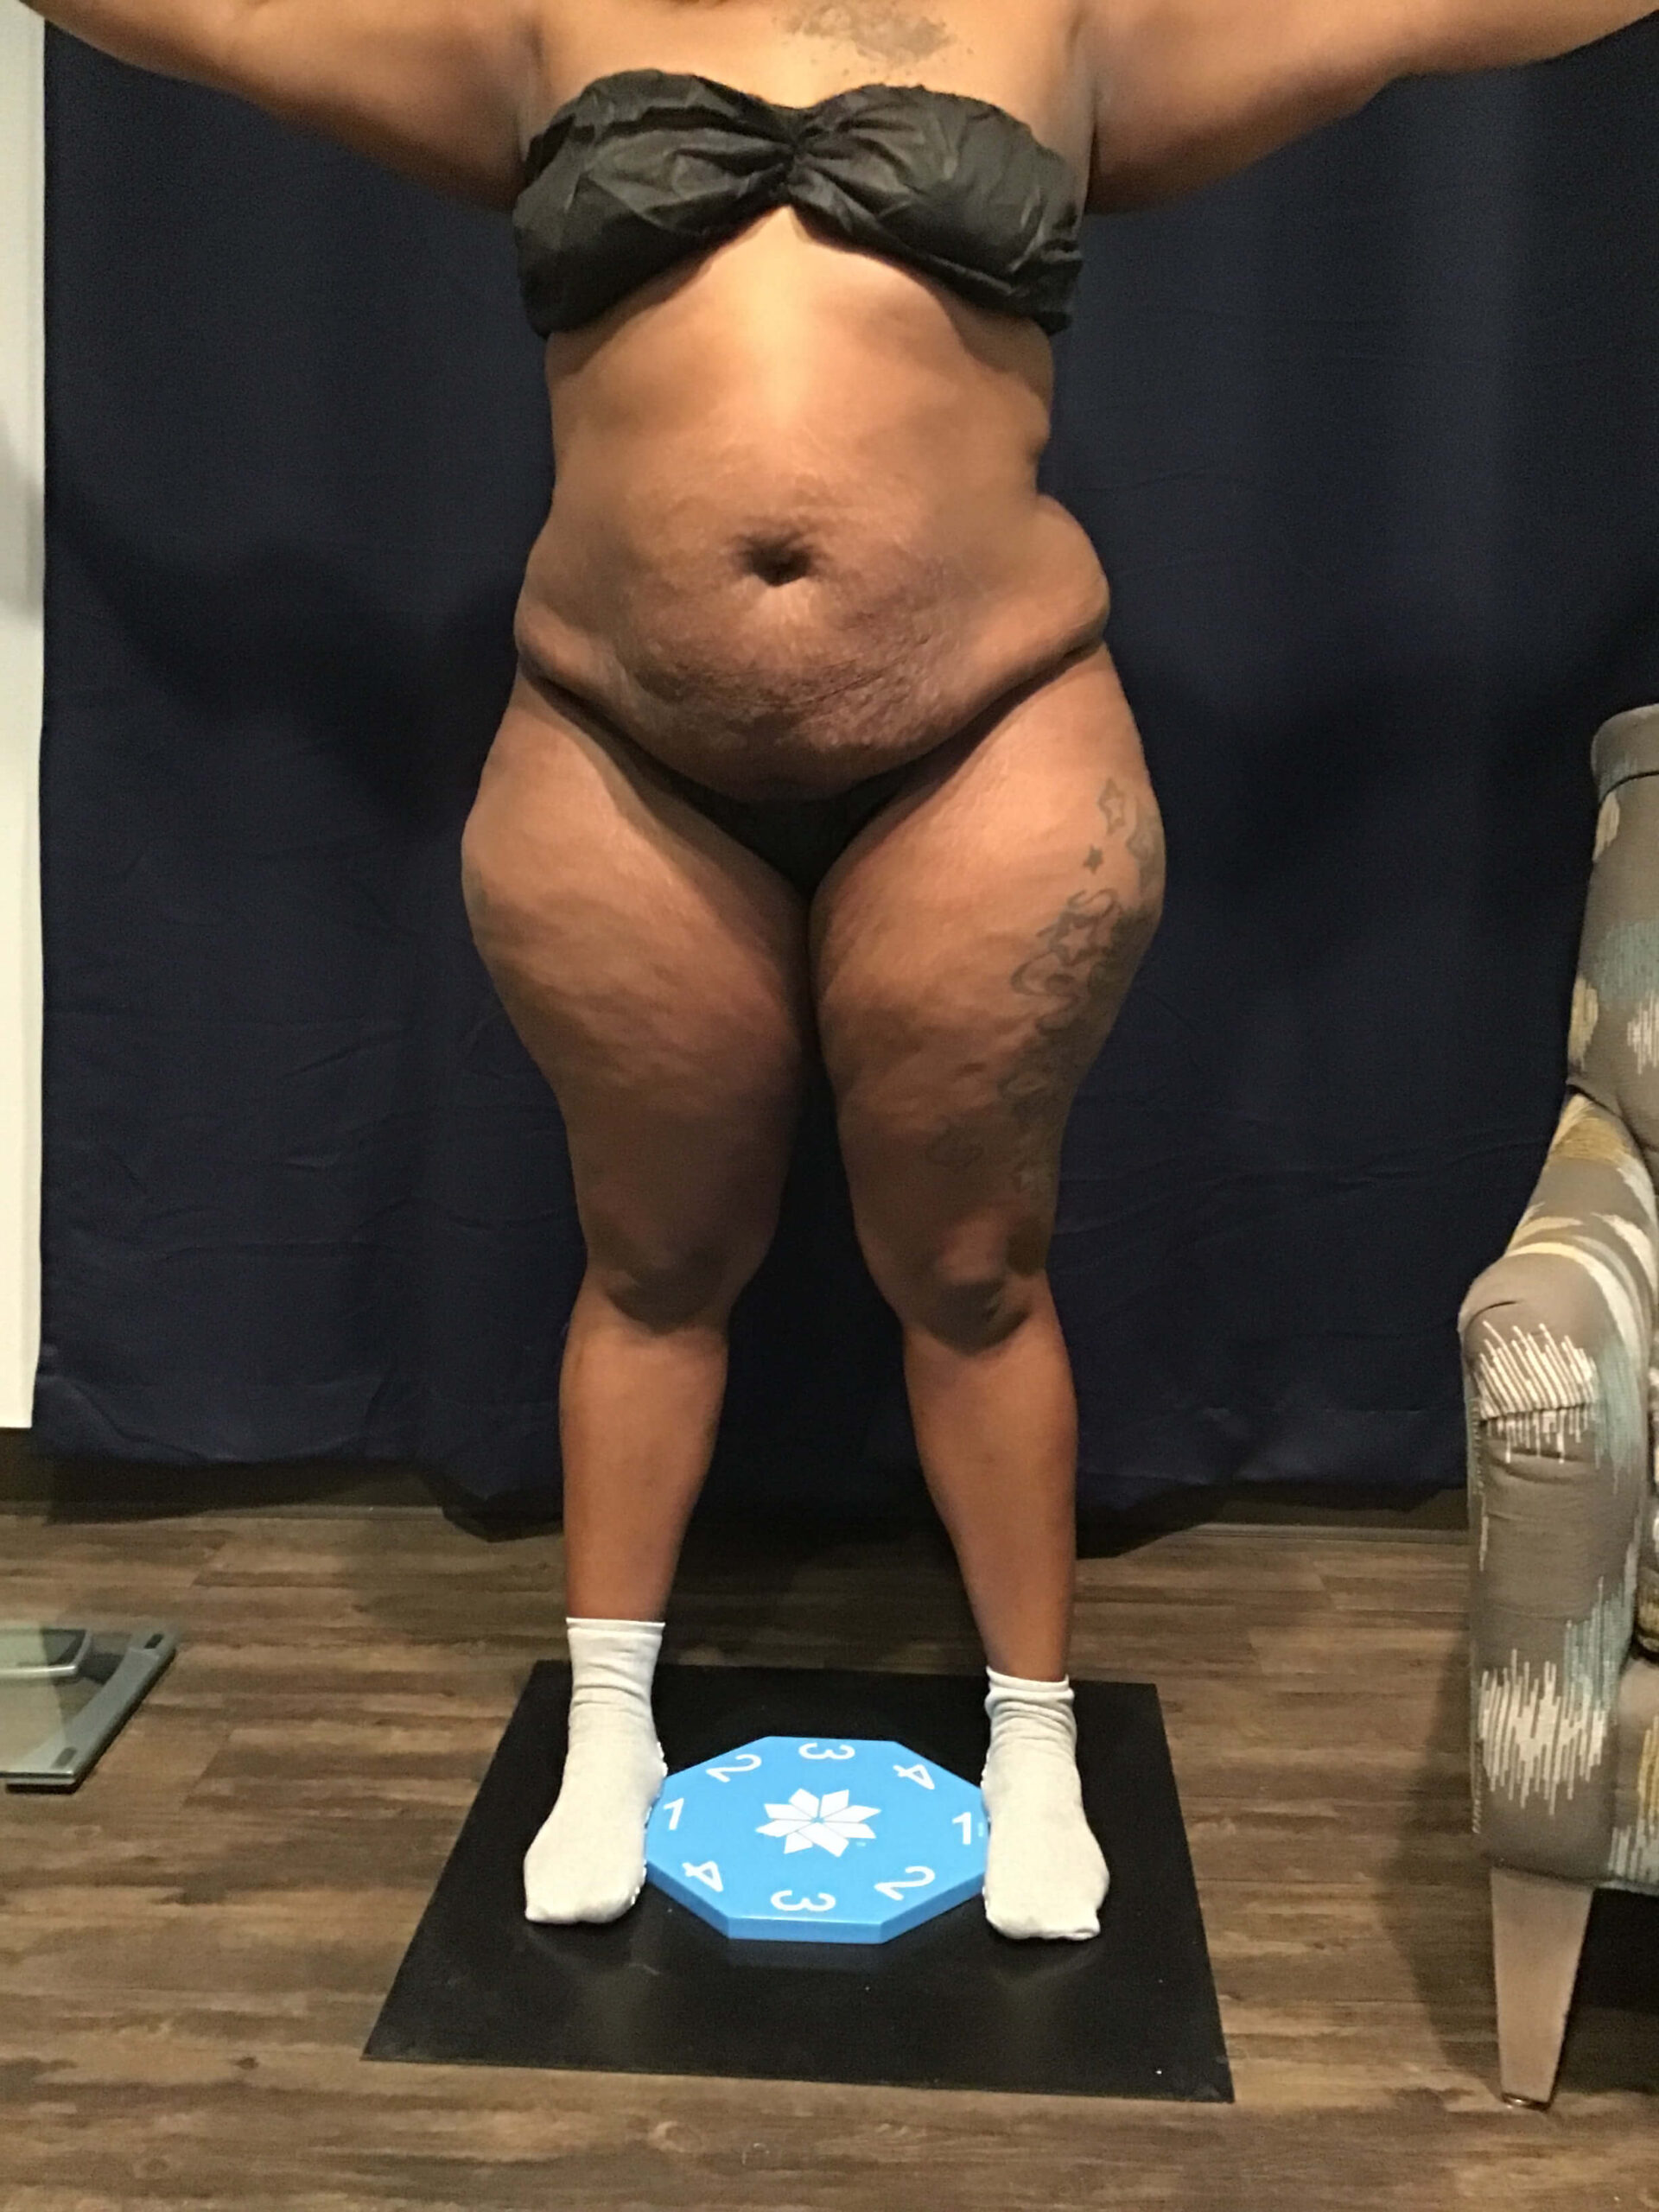
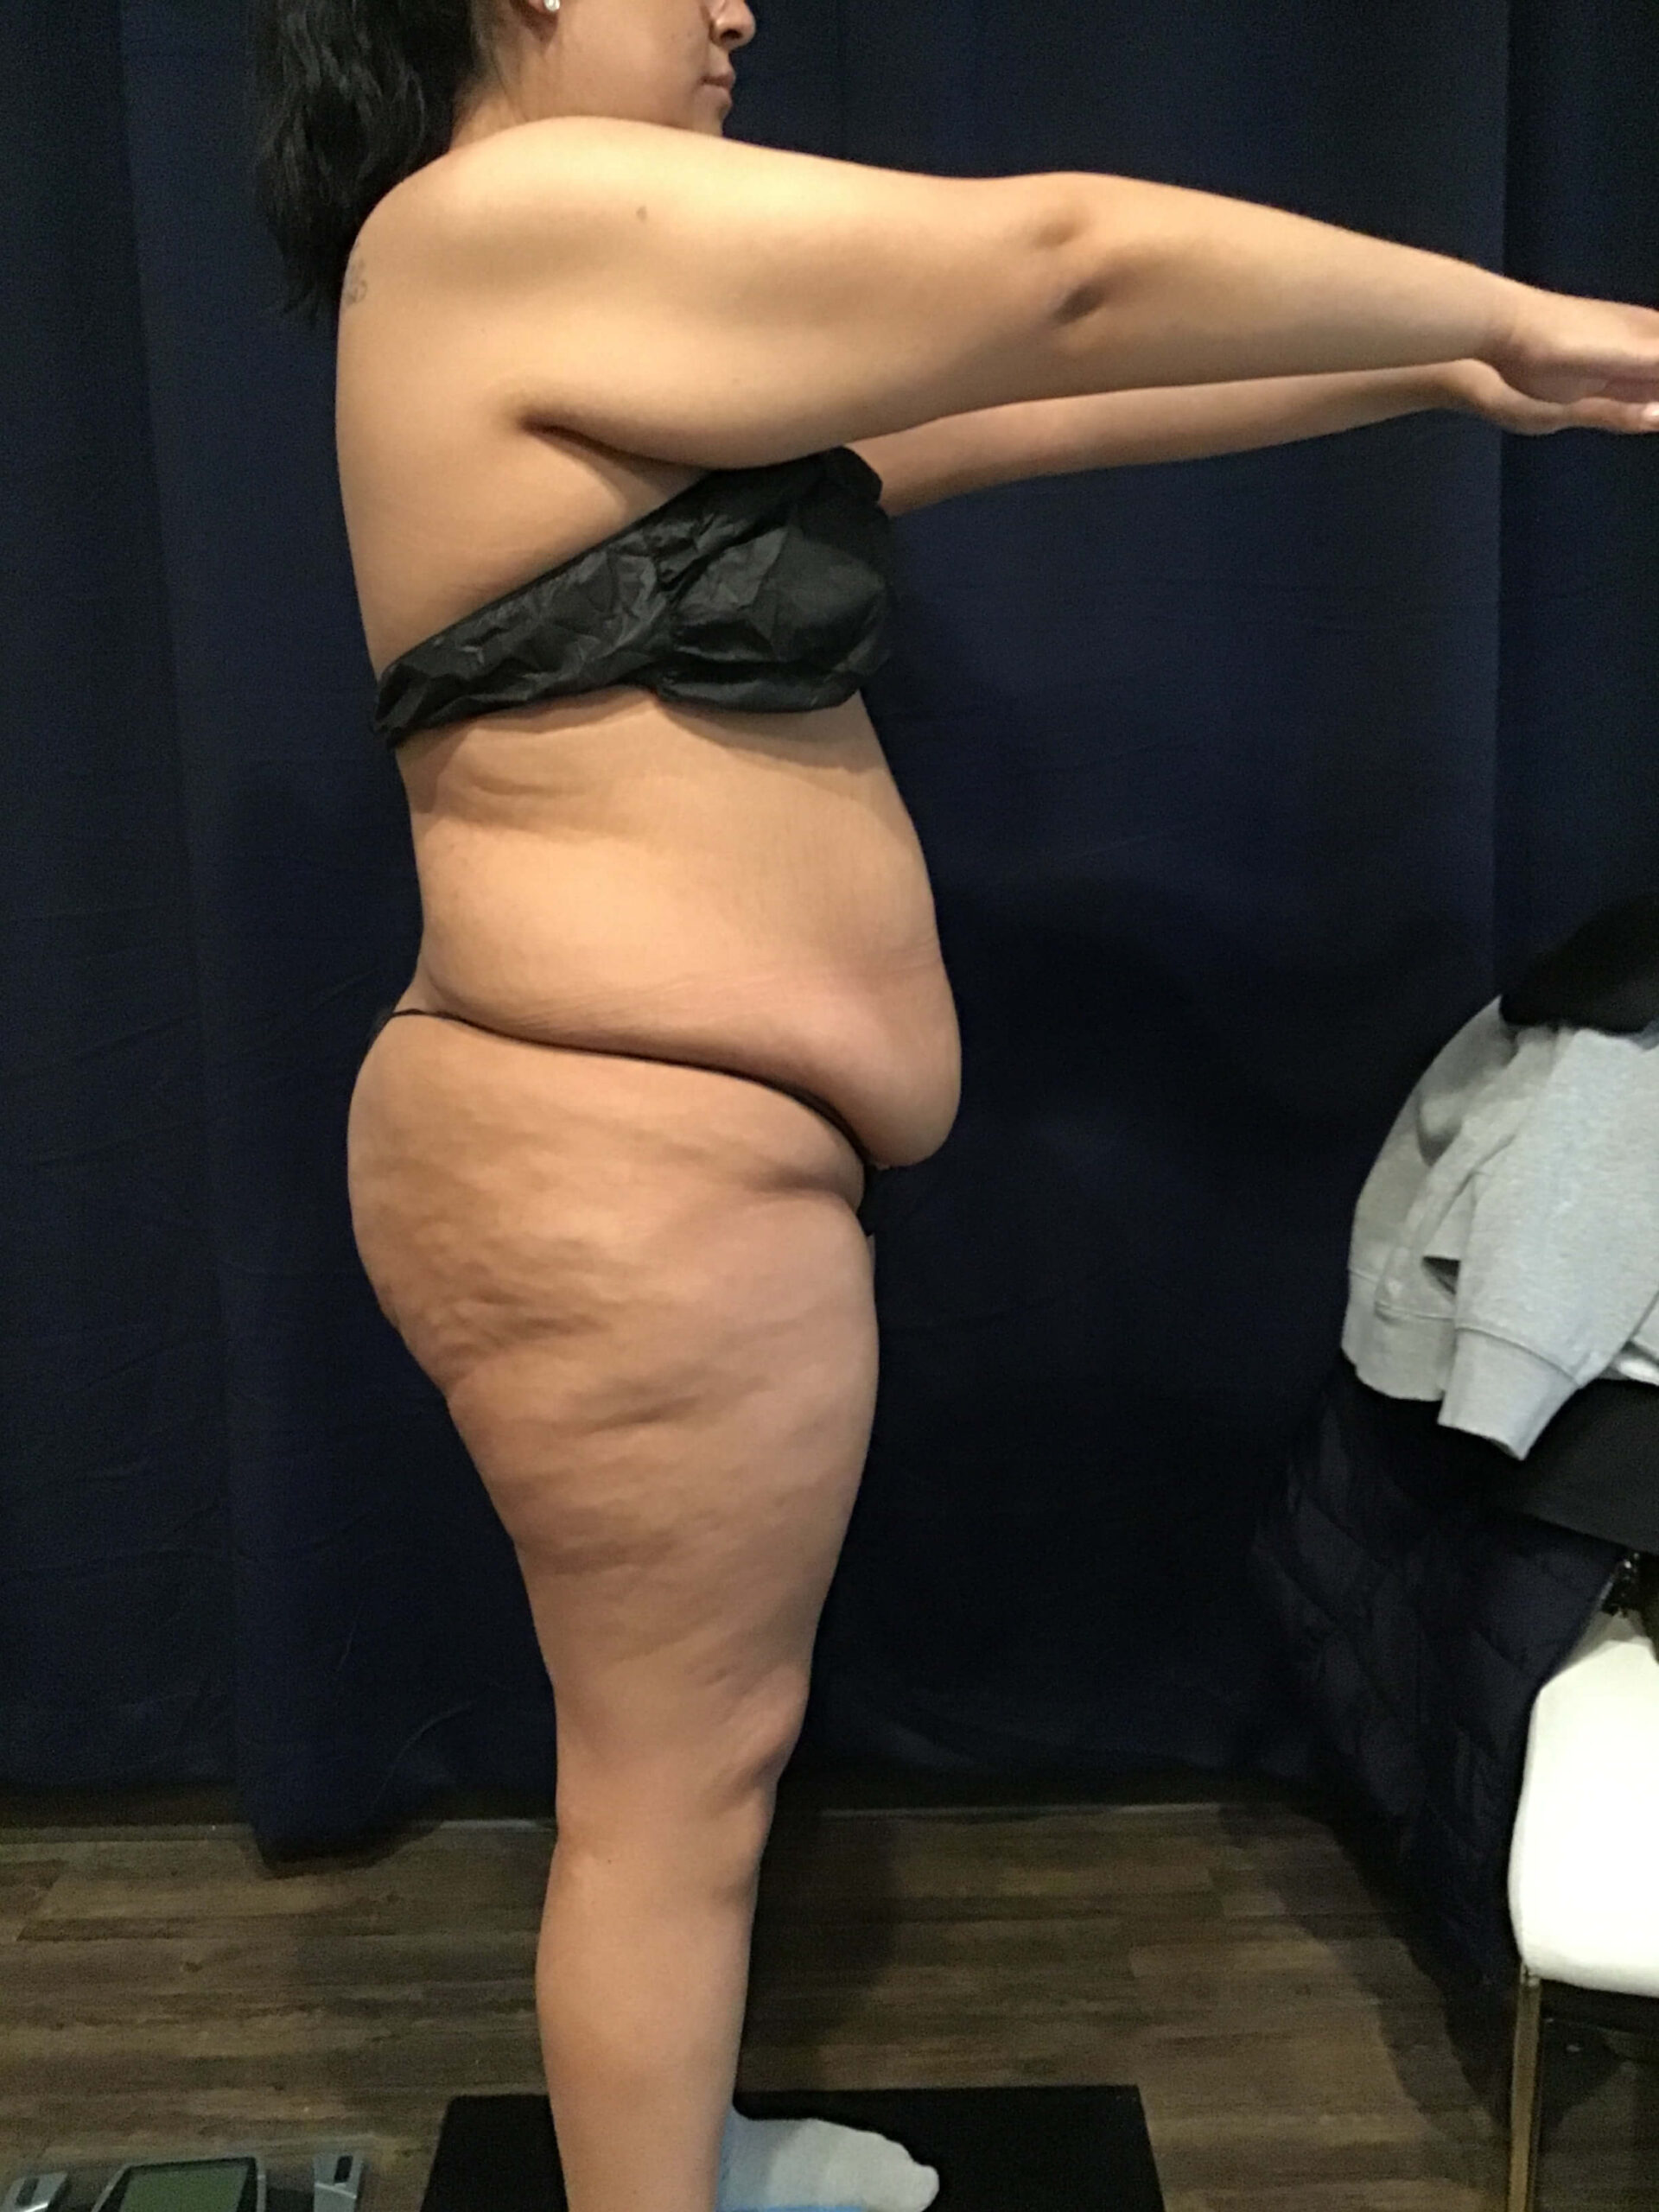
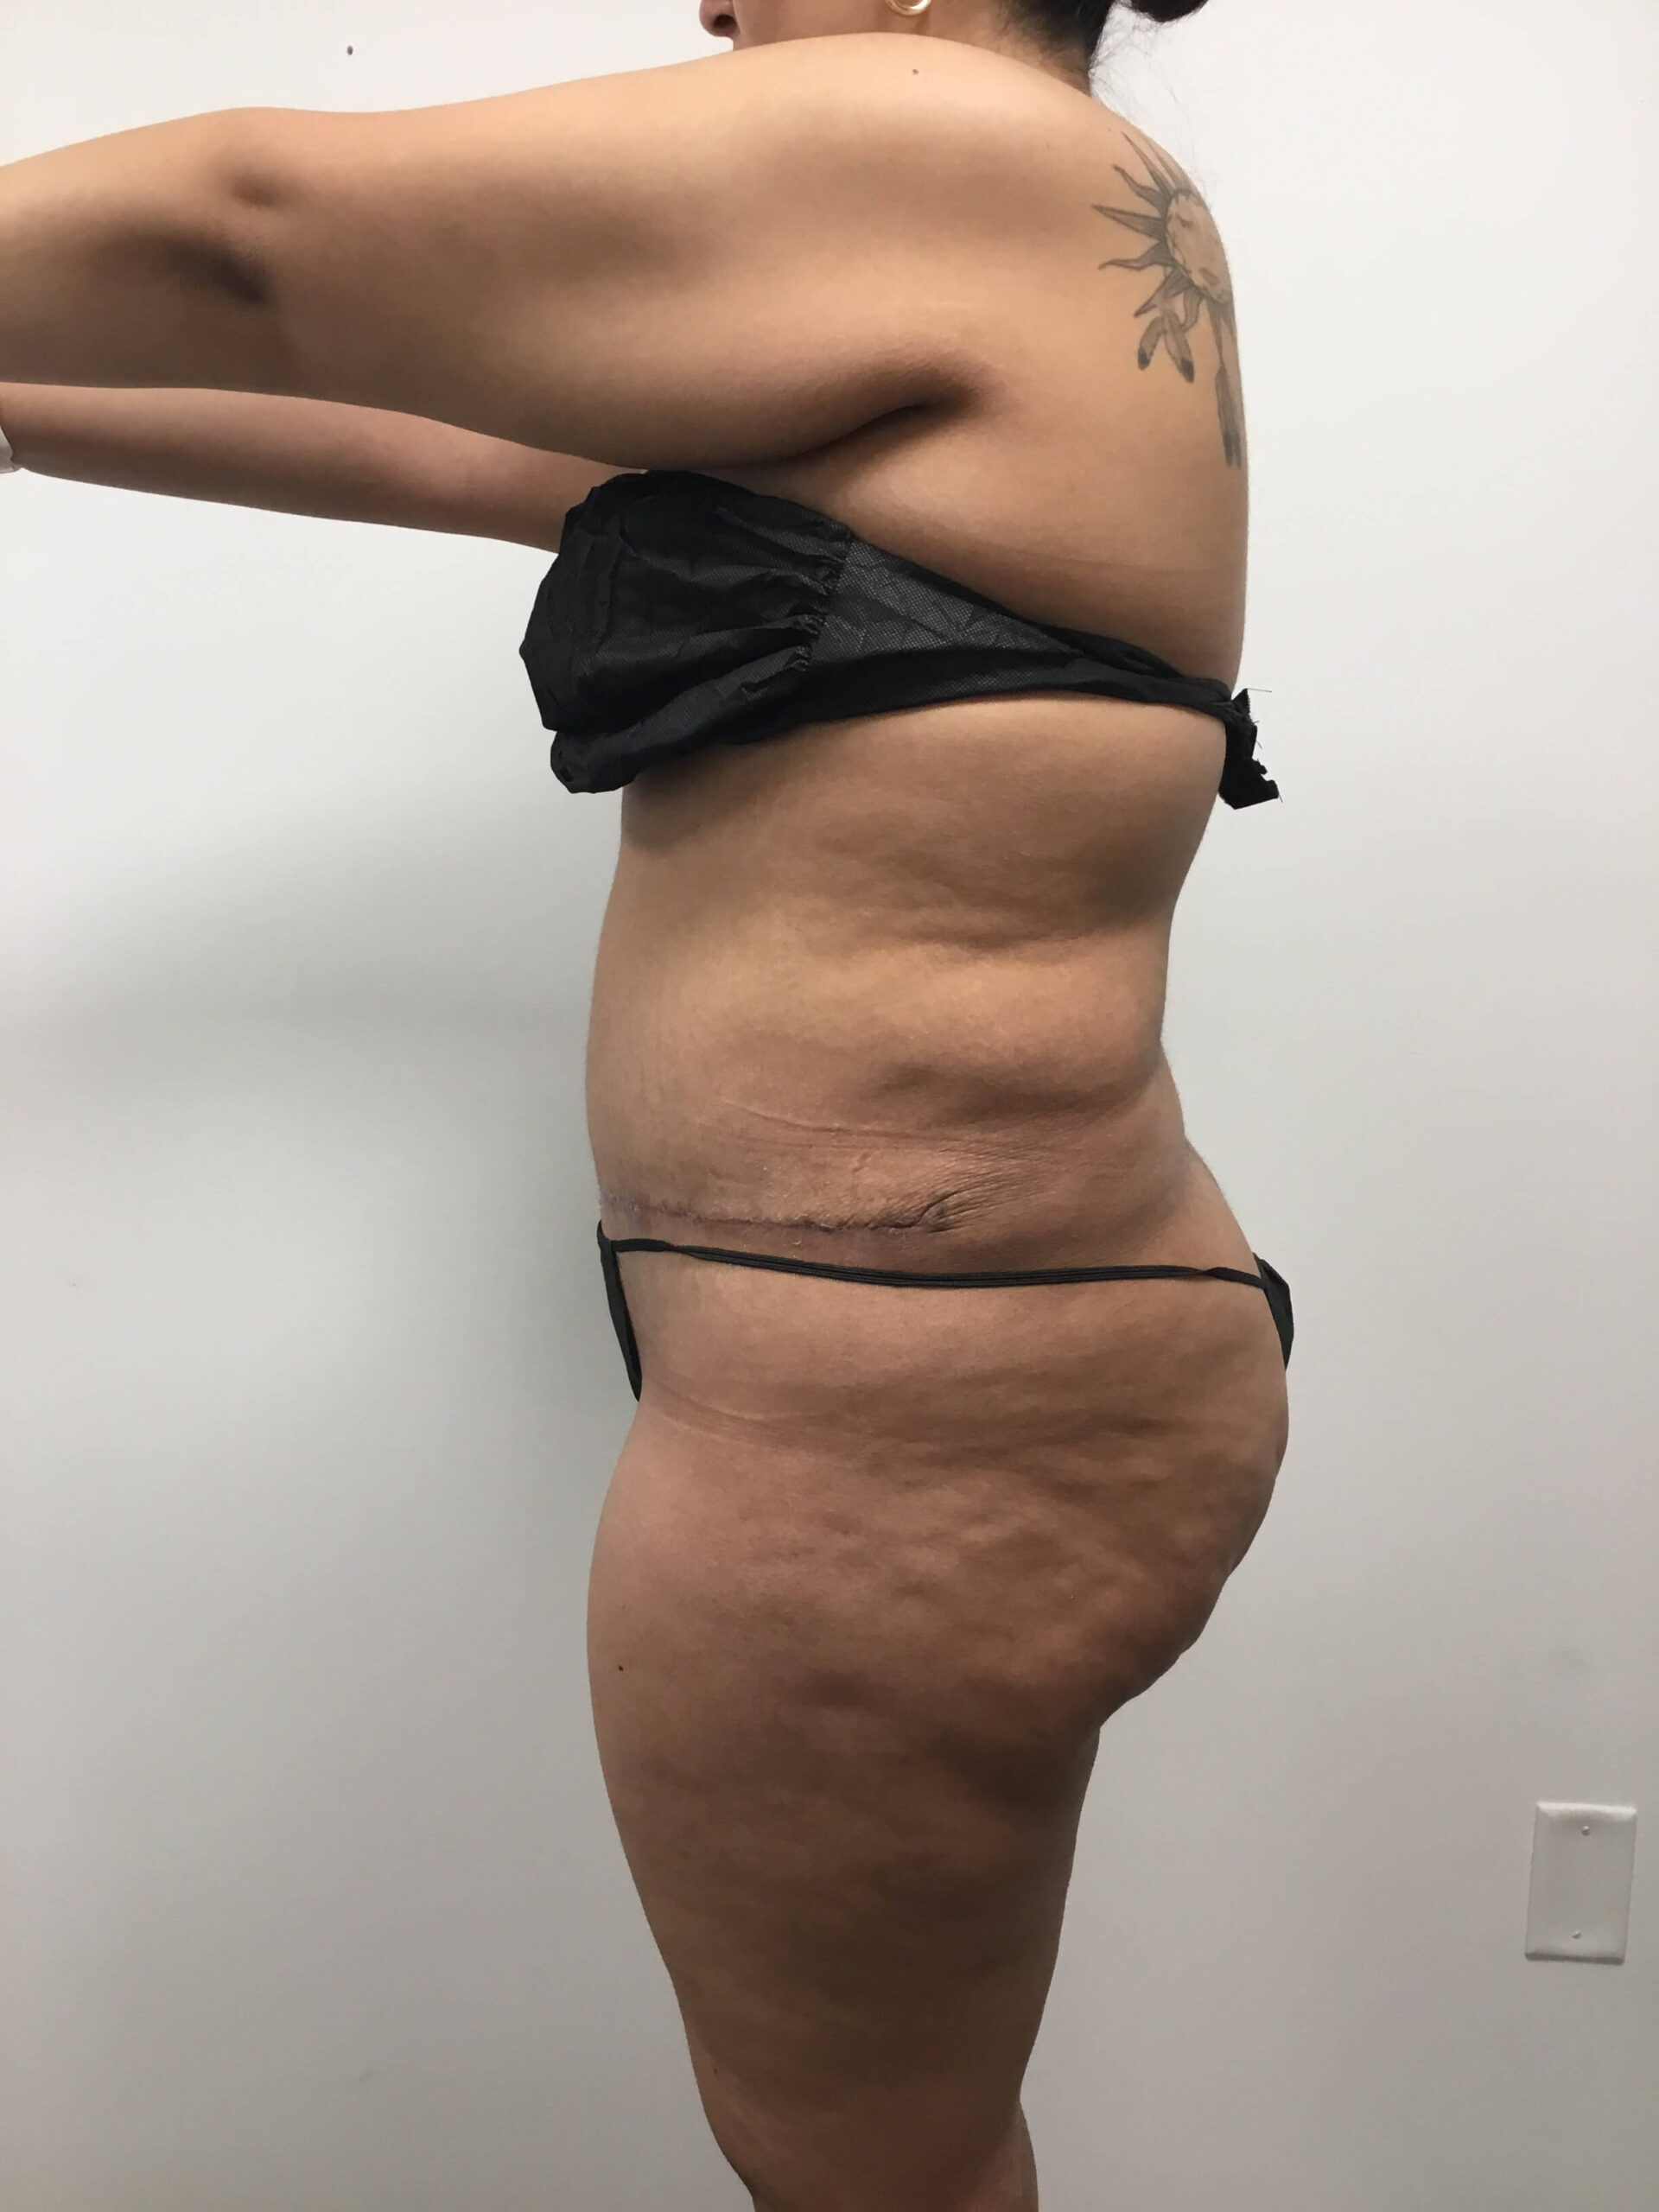
For the Guest Researching Carefully
Choosing a Body Contouring Procedure
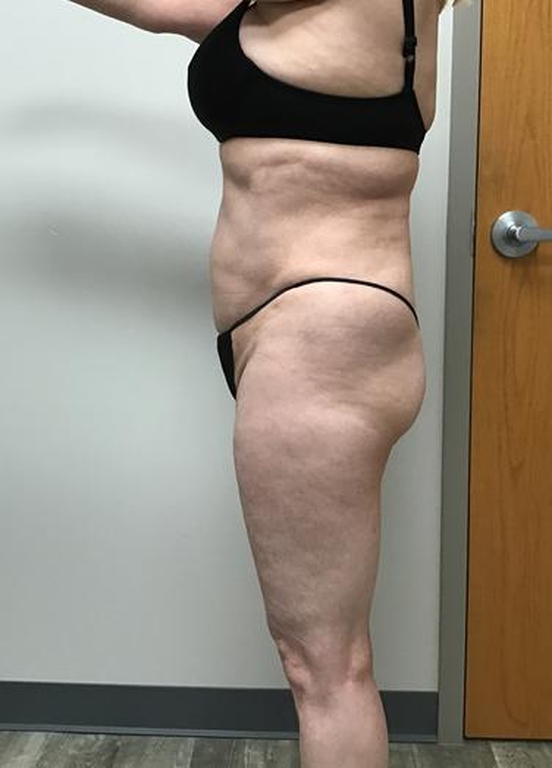
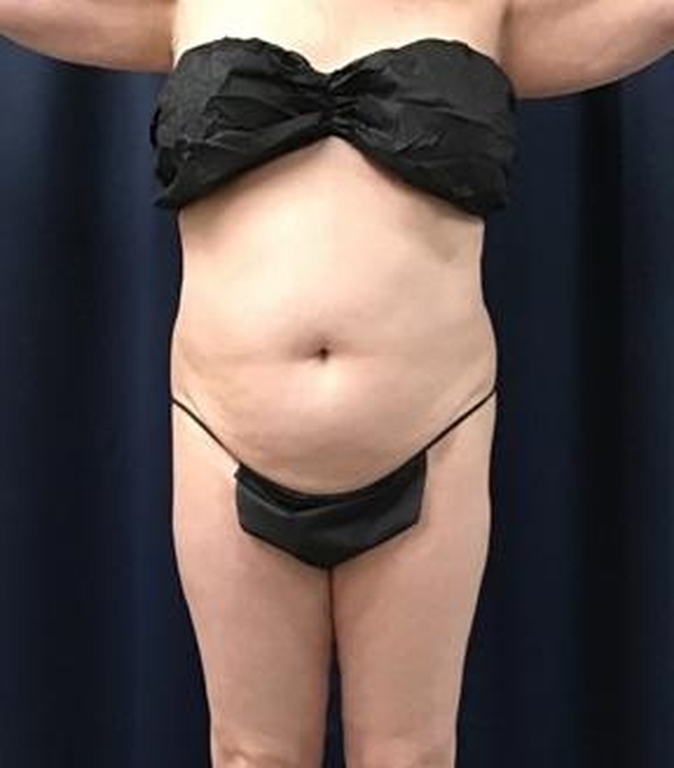
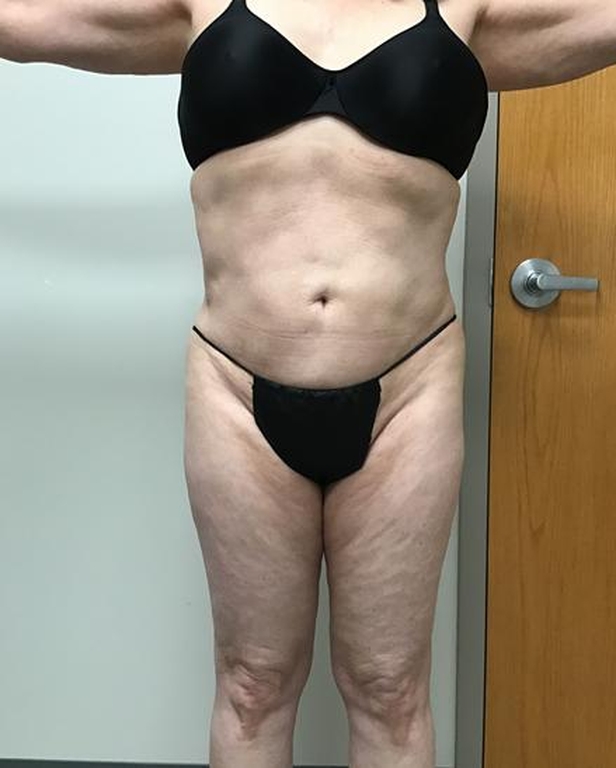
The right procedure is decided by what your body is doing, not by what you arrived asking for. Loose skin, fat distribution and muscle separation each call for a different intervention, and often a combination.
A clinical guide to choosing between TickleLipo, TickleTite, and TickleTuck - based not on procedure names, but on what is actually causing the appearance you want to change.
01 · Premise
Most guests arrive with the wrong procedure in mind.
Most guests come to us thinking they need one procedure and learn at consultation that another is the better answer - or that a combination is. That is not because they did poor research. It is because the cosmetic surgery industry has trained people to shop by procedure name (Brazilian Butt Lift, Mommy Makeover, Tummy Tuck) rather than by what is actually causing the appearance they want to change.
This page is the opposite approach. Instead of asking which procedure are you here for, it asks: what is your body actually doing - and what intervention is matched to it? The clinical logic below is the same logic Dr. Zelko uses in every consultation. Walking through it before you call clarifies your own situation, eliminates several procedures that are not relevant to you, and makes the consultation a conversation between two informed people instead of a sales pitch.
A note before you start: only an in-person physical examination - pinch test, partial crunch, palpation of the linea alba - produces a definitive answer.
02 · Diagnosis
The three causes - and why knowing yours matters.
Before any procedure decision, the question is: what is causing the appearance you want to change? The answer is almost always one of three things, sometimes two, occasionally all three.
01
Subcutaneous Fat
Surgically AddressableThe pinchable fat layer directly beneath the skin and above the muscle. The "love handle." The bra-line bulge. The inner thigh that has resisted every diet you have tried.
Subcutaneous fat is the only cause of body contour change that liposuction - any liposuction - was designed to address. TickleLipo removes subcutaneous fat permanently. This is the procedure that built our practice.
02
Visceral Fat
Not Surgically AddressableThe fat surrounding your internal organs, deep inside the abdominal cavity. You cannot pinch it. You cannot reach it surgically. It is what makes a hard, distended belly that does not soften when you lie down.
No liposuction will address visceral fat. TickleLipo will not. VASER will not. SmartLipo will not. A tummy tuck will not. Visceral fat requires metabolic intervention - and the most clinically effective intervention currently available is GLP-1 medication, which demonstrates preferential reduction of visceral fat compared to subcutaneous fat. This practice offers a medically supervised in-house GLP-1 program (semaglutide and tirzepatide) led by Sydney Zelko RN and Gianna Giuntoli RN under Dr. Zelko's direct physician oversight, structured around body composition rather than scale weight alone. If visceral fat is your primary concern, the GLP-1 program is the right starting point - and the same practice that manages your weight loss is the one that performs the body contouring after, when contouring is needed. See our GLP-1 Medical Weight Loss page
03
Loose Skin and Tissue
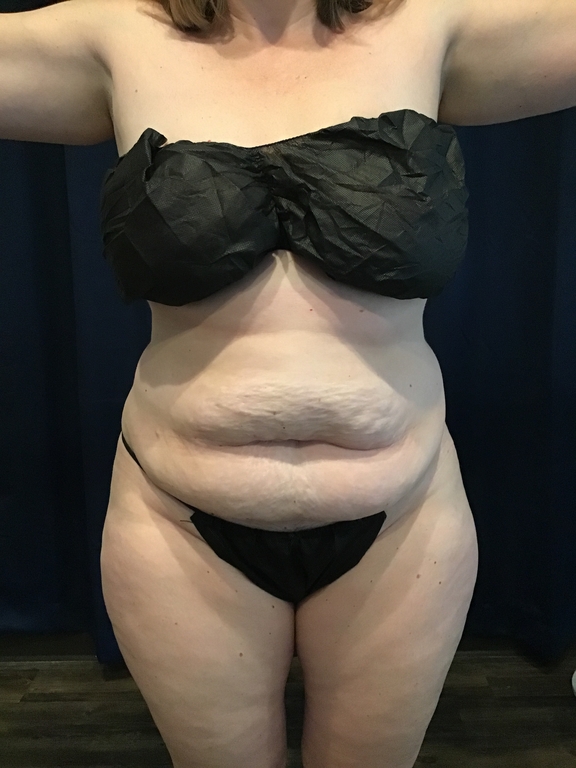
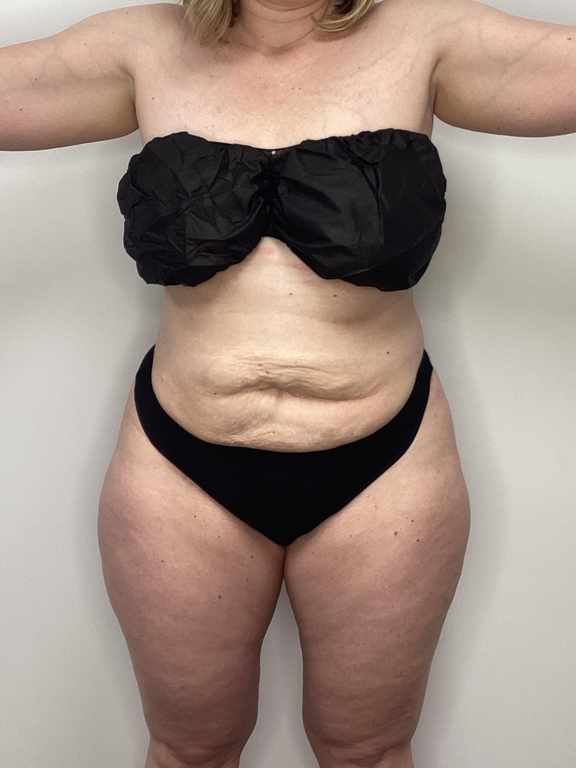
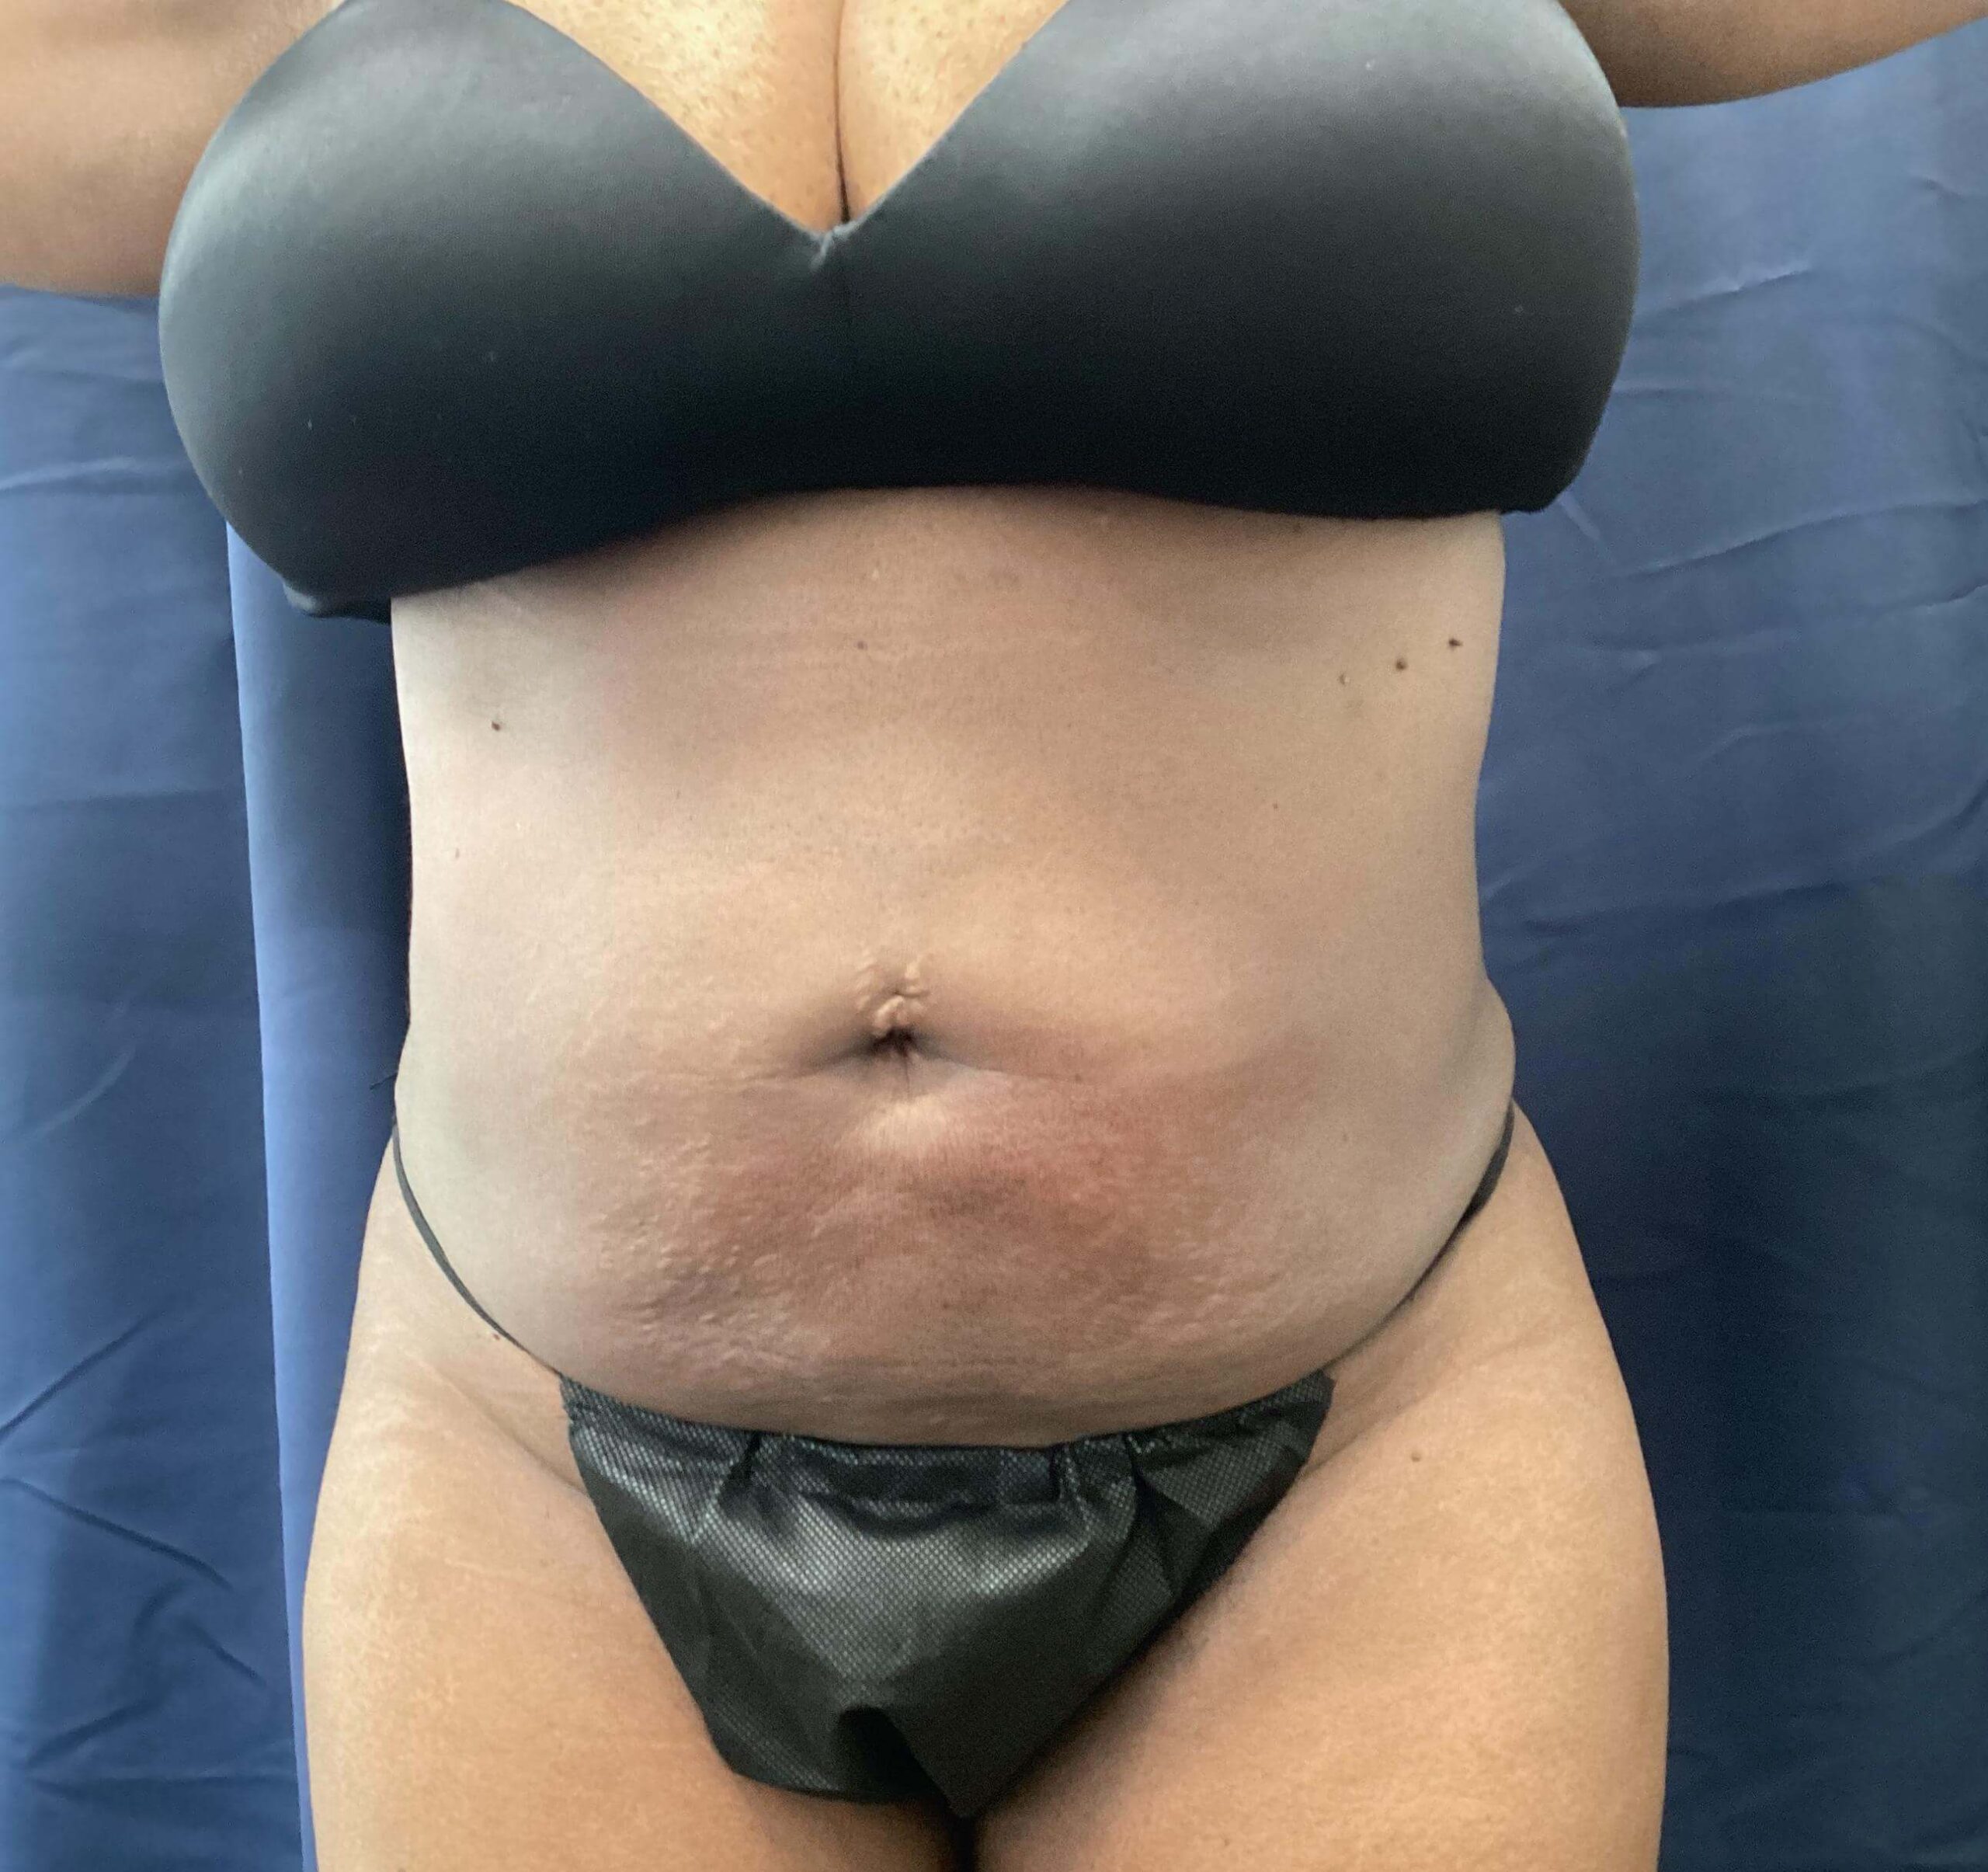
Surgically AddressableSkin that no longer retracts the way it used to. The post-pregnancy apron. The flat-stomach-but-loose-pouch result of significant weight loss. The hanging skin that chronically chafes. Loose skin has a different mechanism than fat - it is a structural problem, not a volume problem - and the procedure choice depends entirely on how much loose skin is present.
This category includes a wide spectrum: post-pregnancy mothers with stubborn lower abdominal laxity, GLP-1 patients who lost 30–80 lbs, lifestyle weight-loss guests who lost 100–150 lbs, and post-bariatric guests who lost 150 to 250+ lbs through gastric bypass or sleeve gastrectomy. All of these are routinely treated at this practice.
04
A Special Case: Diastasis Recti
Coordinated Care RequiredThe separation of the paired abdominal muscles along the midline, common after pregnancy. Diastasis is not fat and it is not skin - it is muscle architecture. TickleLipo can make the appearance of diastasis worse, because removing the subcutaneous fat that masked the separation makes the underlying muscle gap more visible, not less.
If clinically significant diastasis (over 3 cm) is your primary issue, plication is the answer, not liposuction. Plication cases are currently referred to a plastic surgeon - they handle the case from there. No coordination, no joint care plan, no shared management. We refer the case out cleanly. In 2027, Dr. Ian Zelko brings plication capability in-house.
The right answer for your body - even when the right answer is "not this practice, not yet, or not at all."
Dr. Zelko's Standard
03 · Treatment
The three procedures - matched to cause.
Each procedure is matched to a specific clinical situation. Reading horizontally - situation, procedure, what it does, what it won't do - gives you a complete picture of where each one fits.
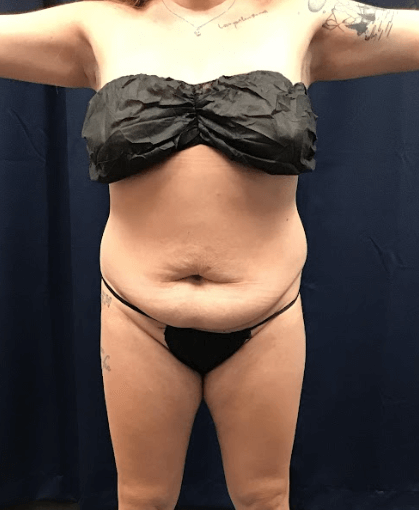
Subcutaneous fat in defined areas. Skin elasticity is good. You want contouring, not skin removal.
TickleLipoAwake liposculpture · 3.5mm cannula · 1–2 day recovery
What it does
Permanently removes subcutaneous fat through a 3.5mm incision. Awake, local anesthesia, same-day home, 1–2 day recovery.
What it won't do
Will not tighten significantly loose skin. Will not address muscle separation. Will not remove visceral fat.
Mild-to-moderate skin laxity. Not enough loose skin to justify a tuck, but more than fat removal alone will fix. Pinch test reveals laxity that pulls back into place when released.
TickleTiteTickleLipo + Renuvion radiofrequency · skin tightening
What it does
Combines fat removal with radiofrequency-assisted skin tightening. Awake, local anesthesia, same-day home.
What it won't do
Will reduce skin laxity by no more than half. If you want "tight as a drum," this is not enough.
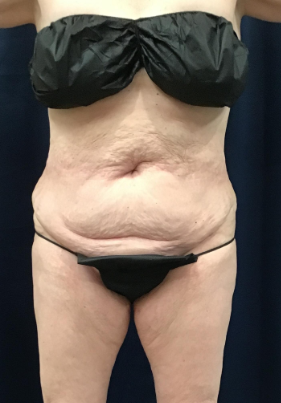
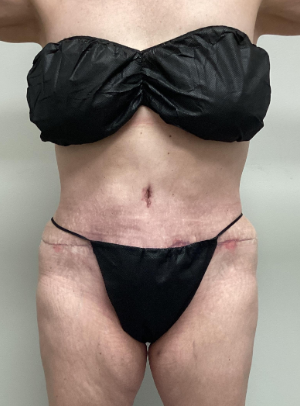
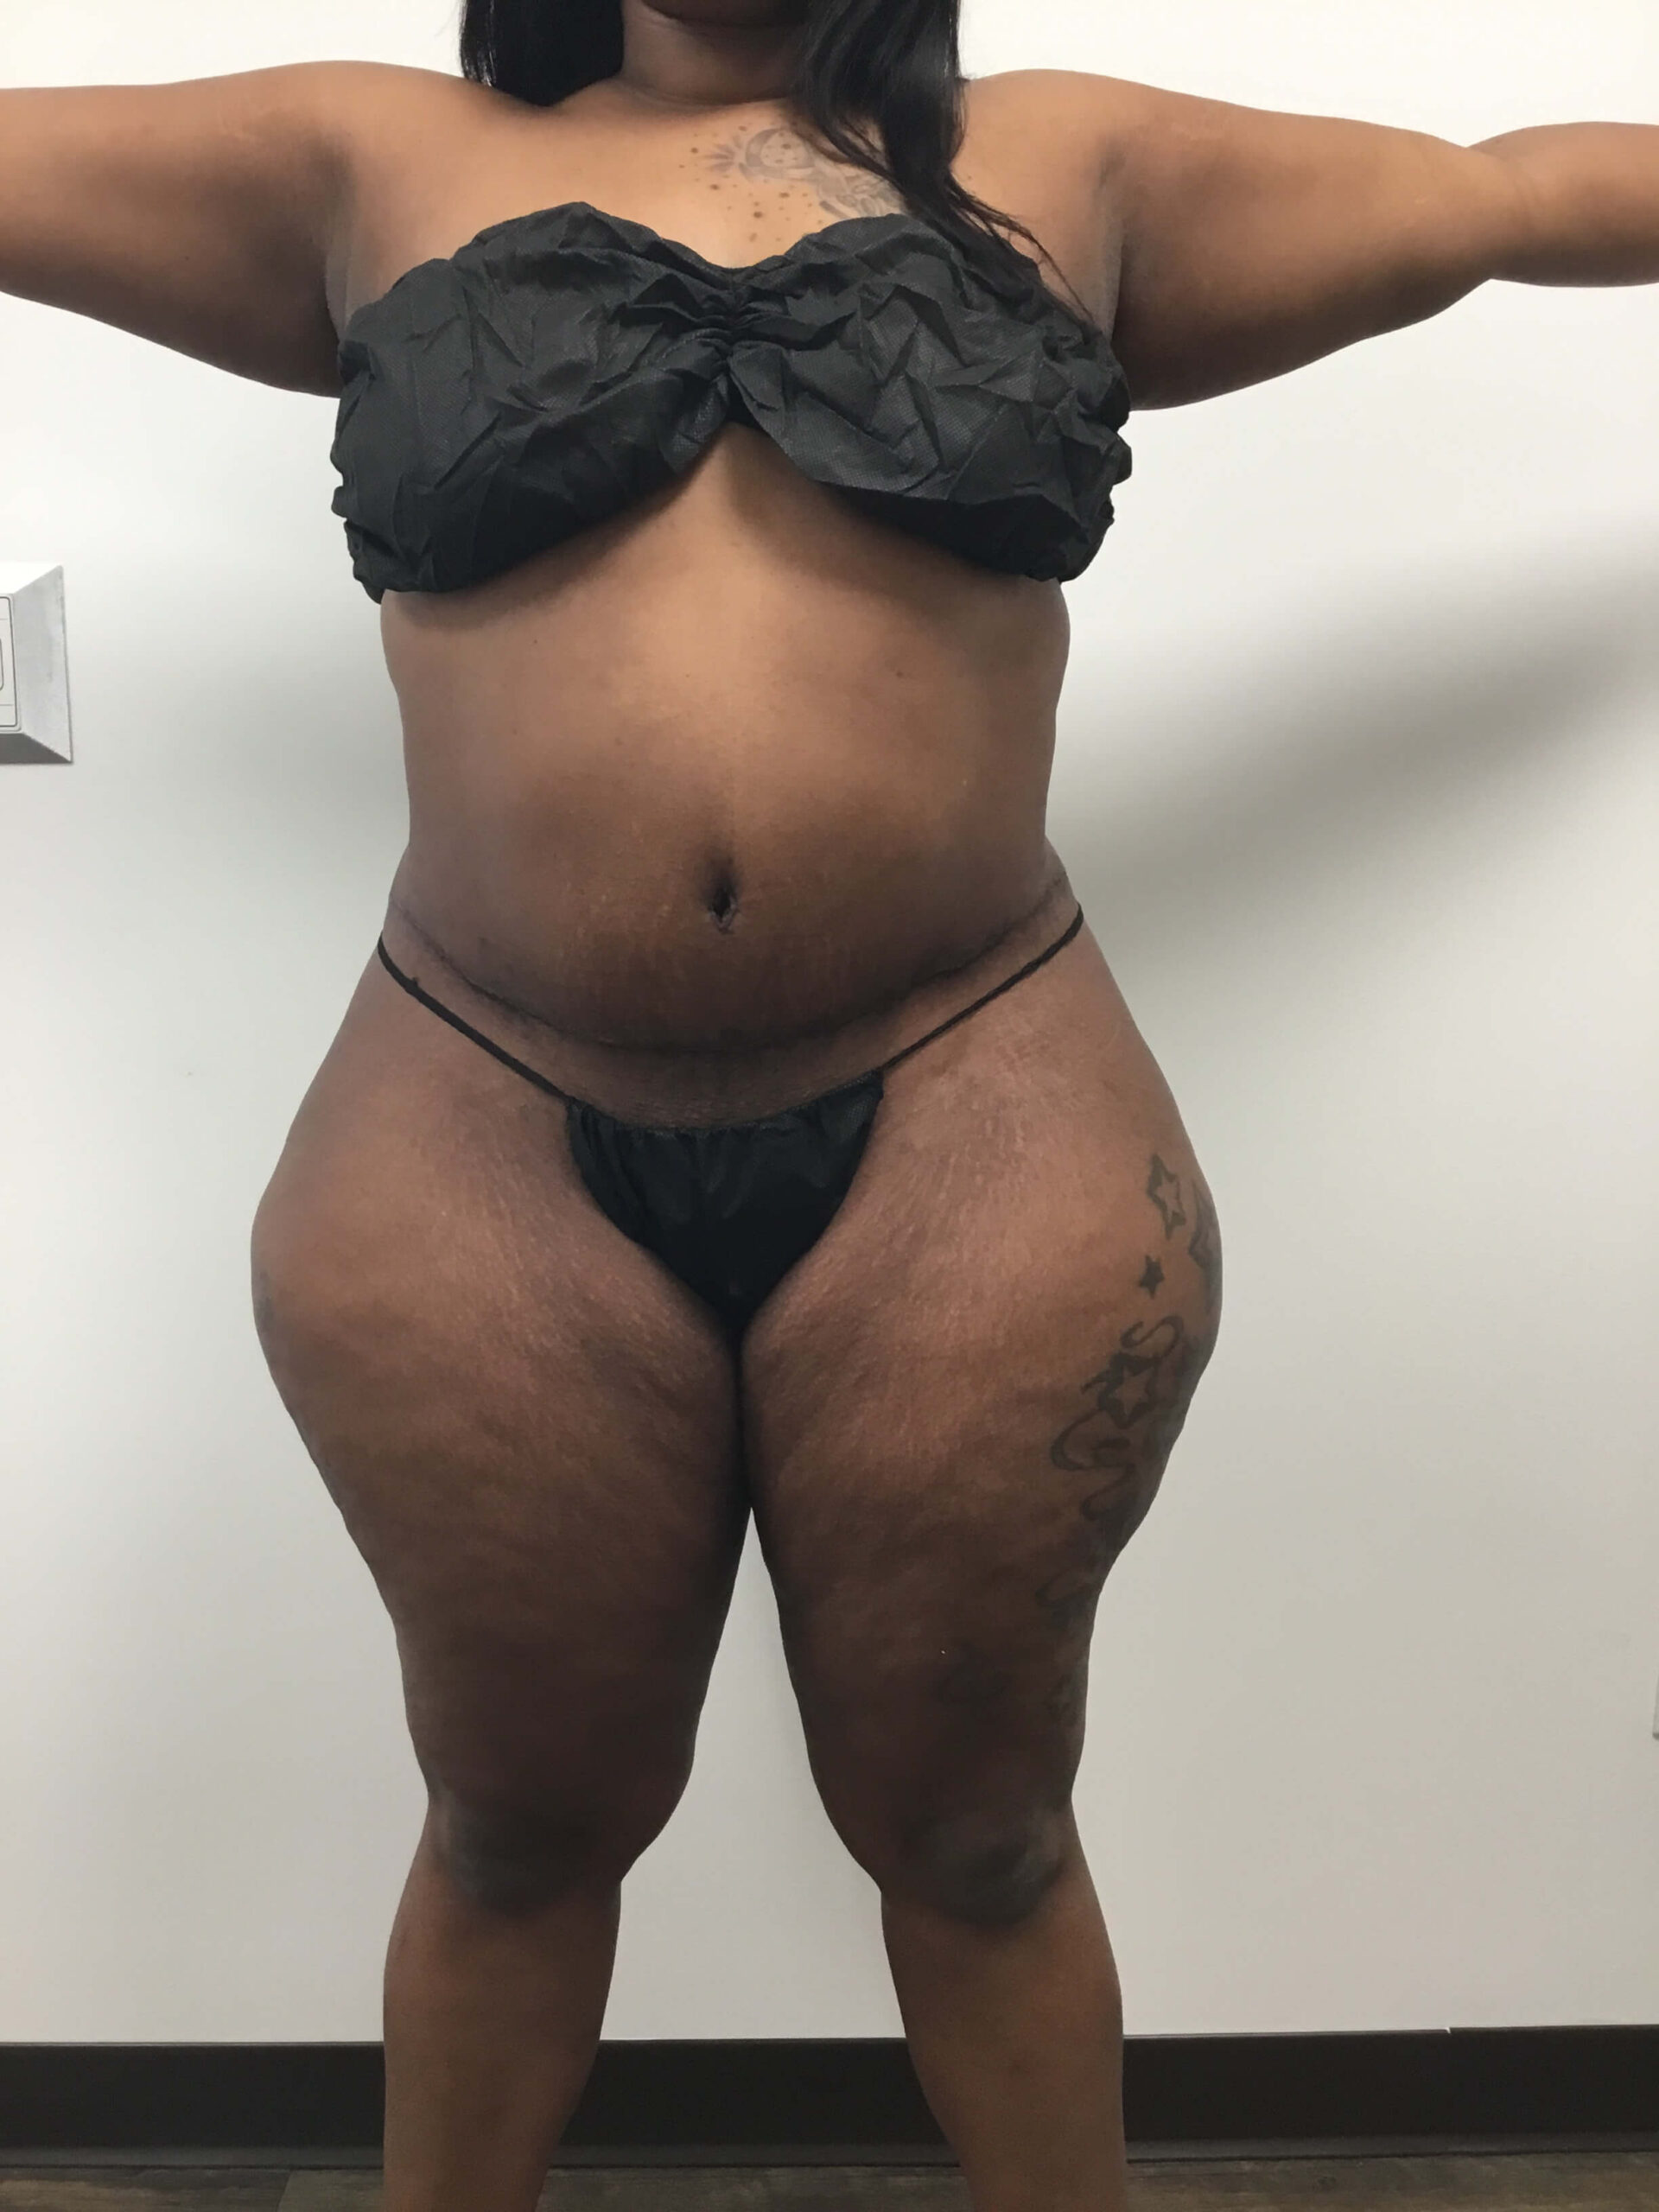
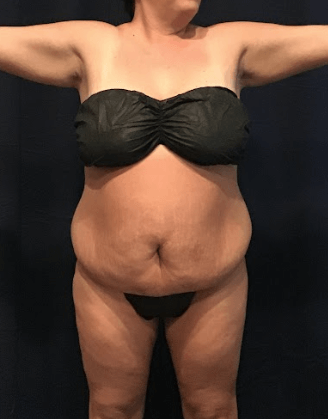
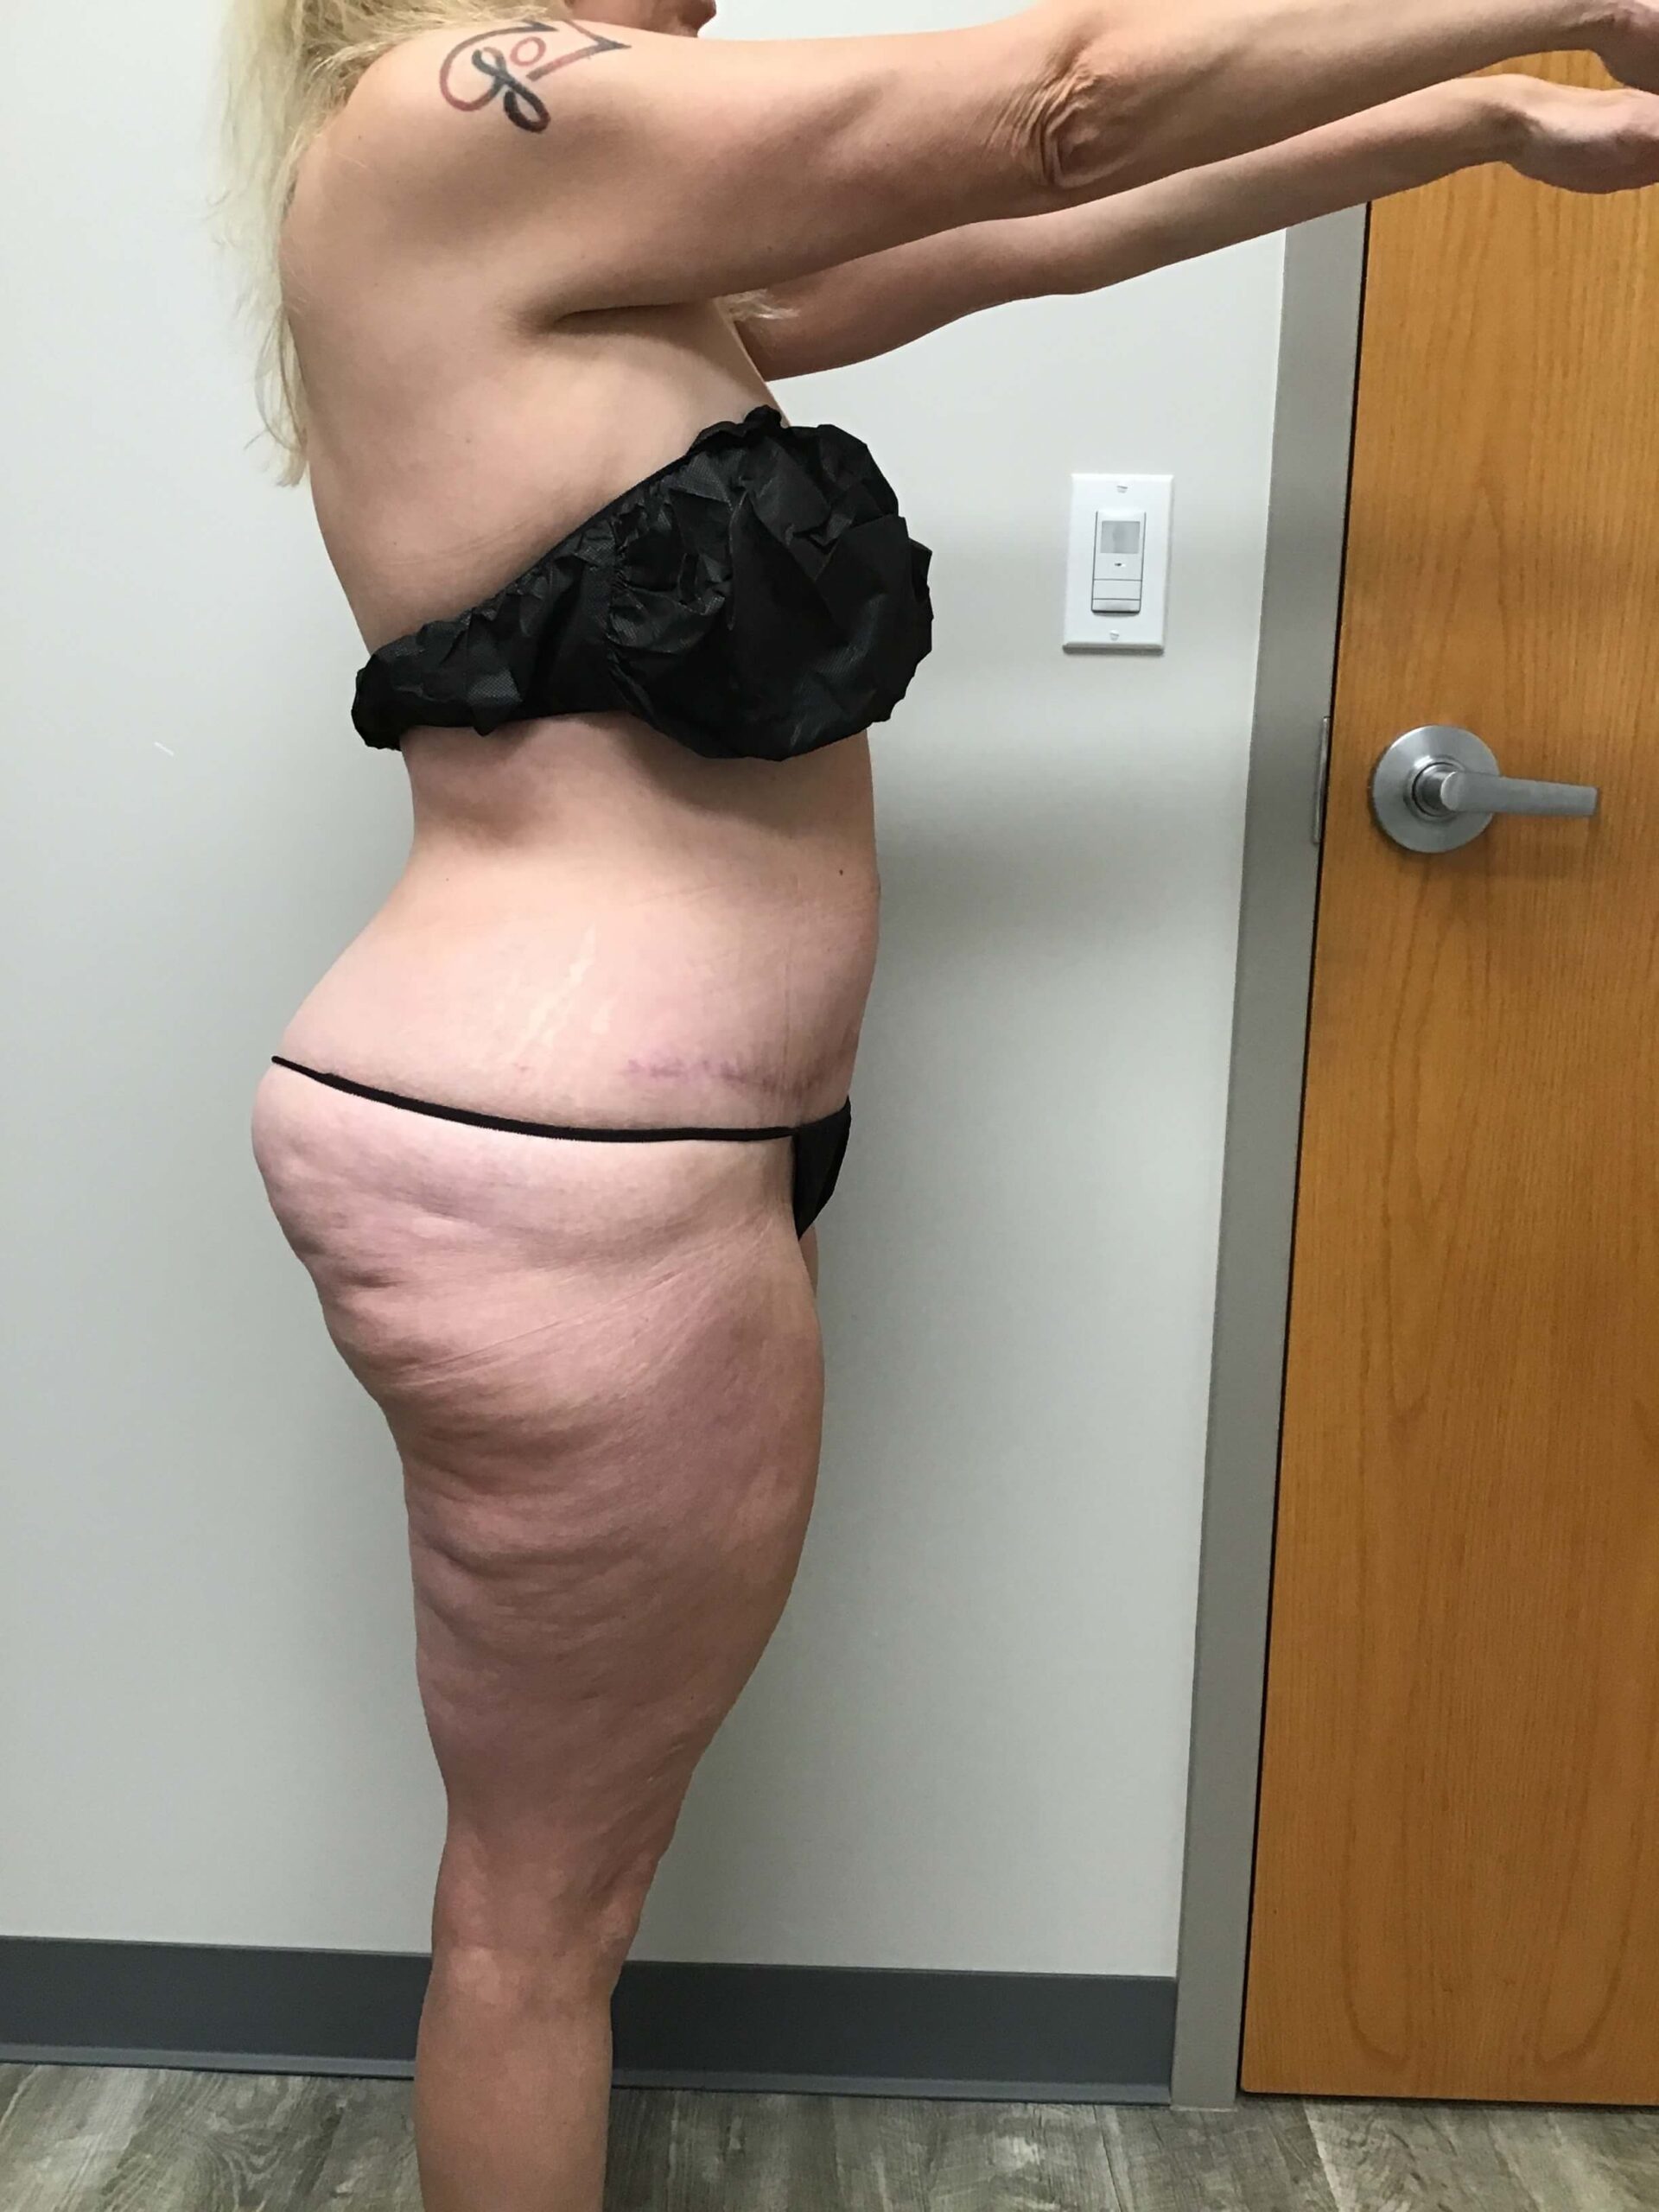
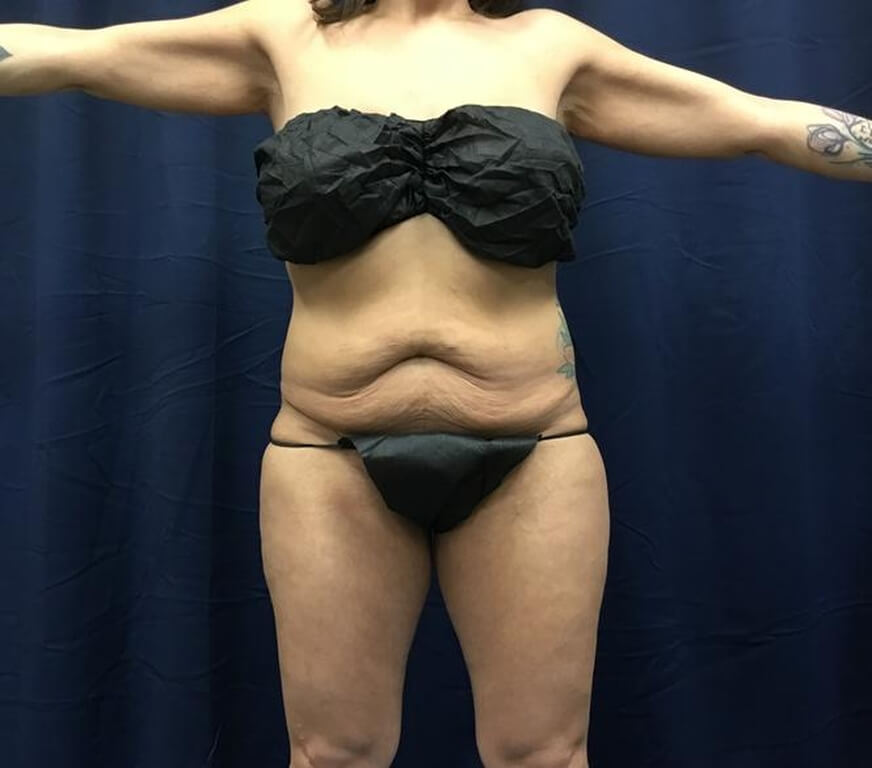
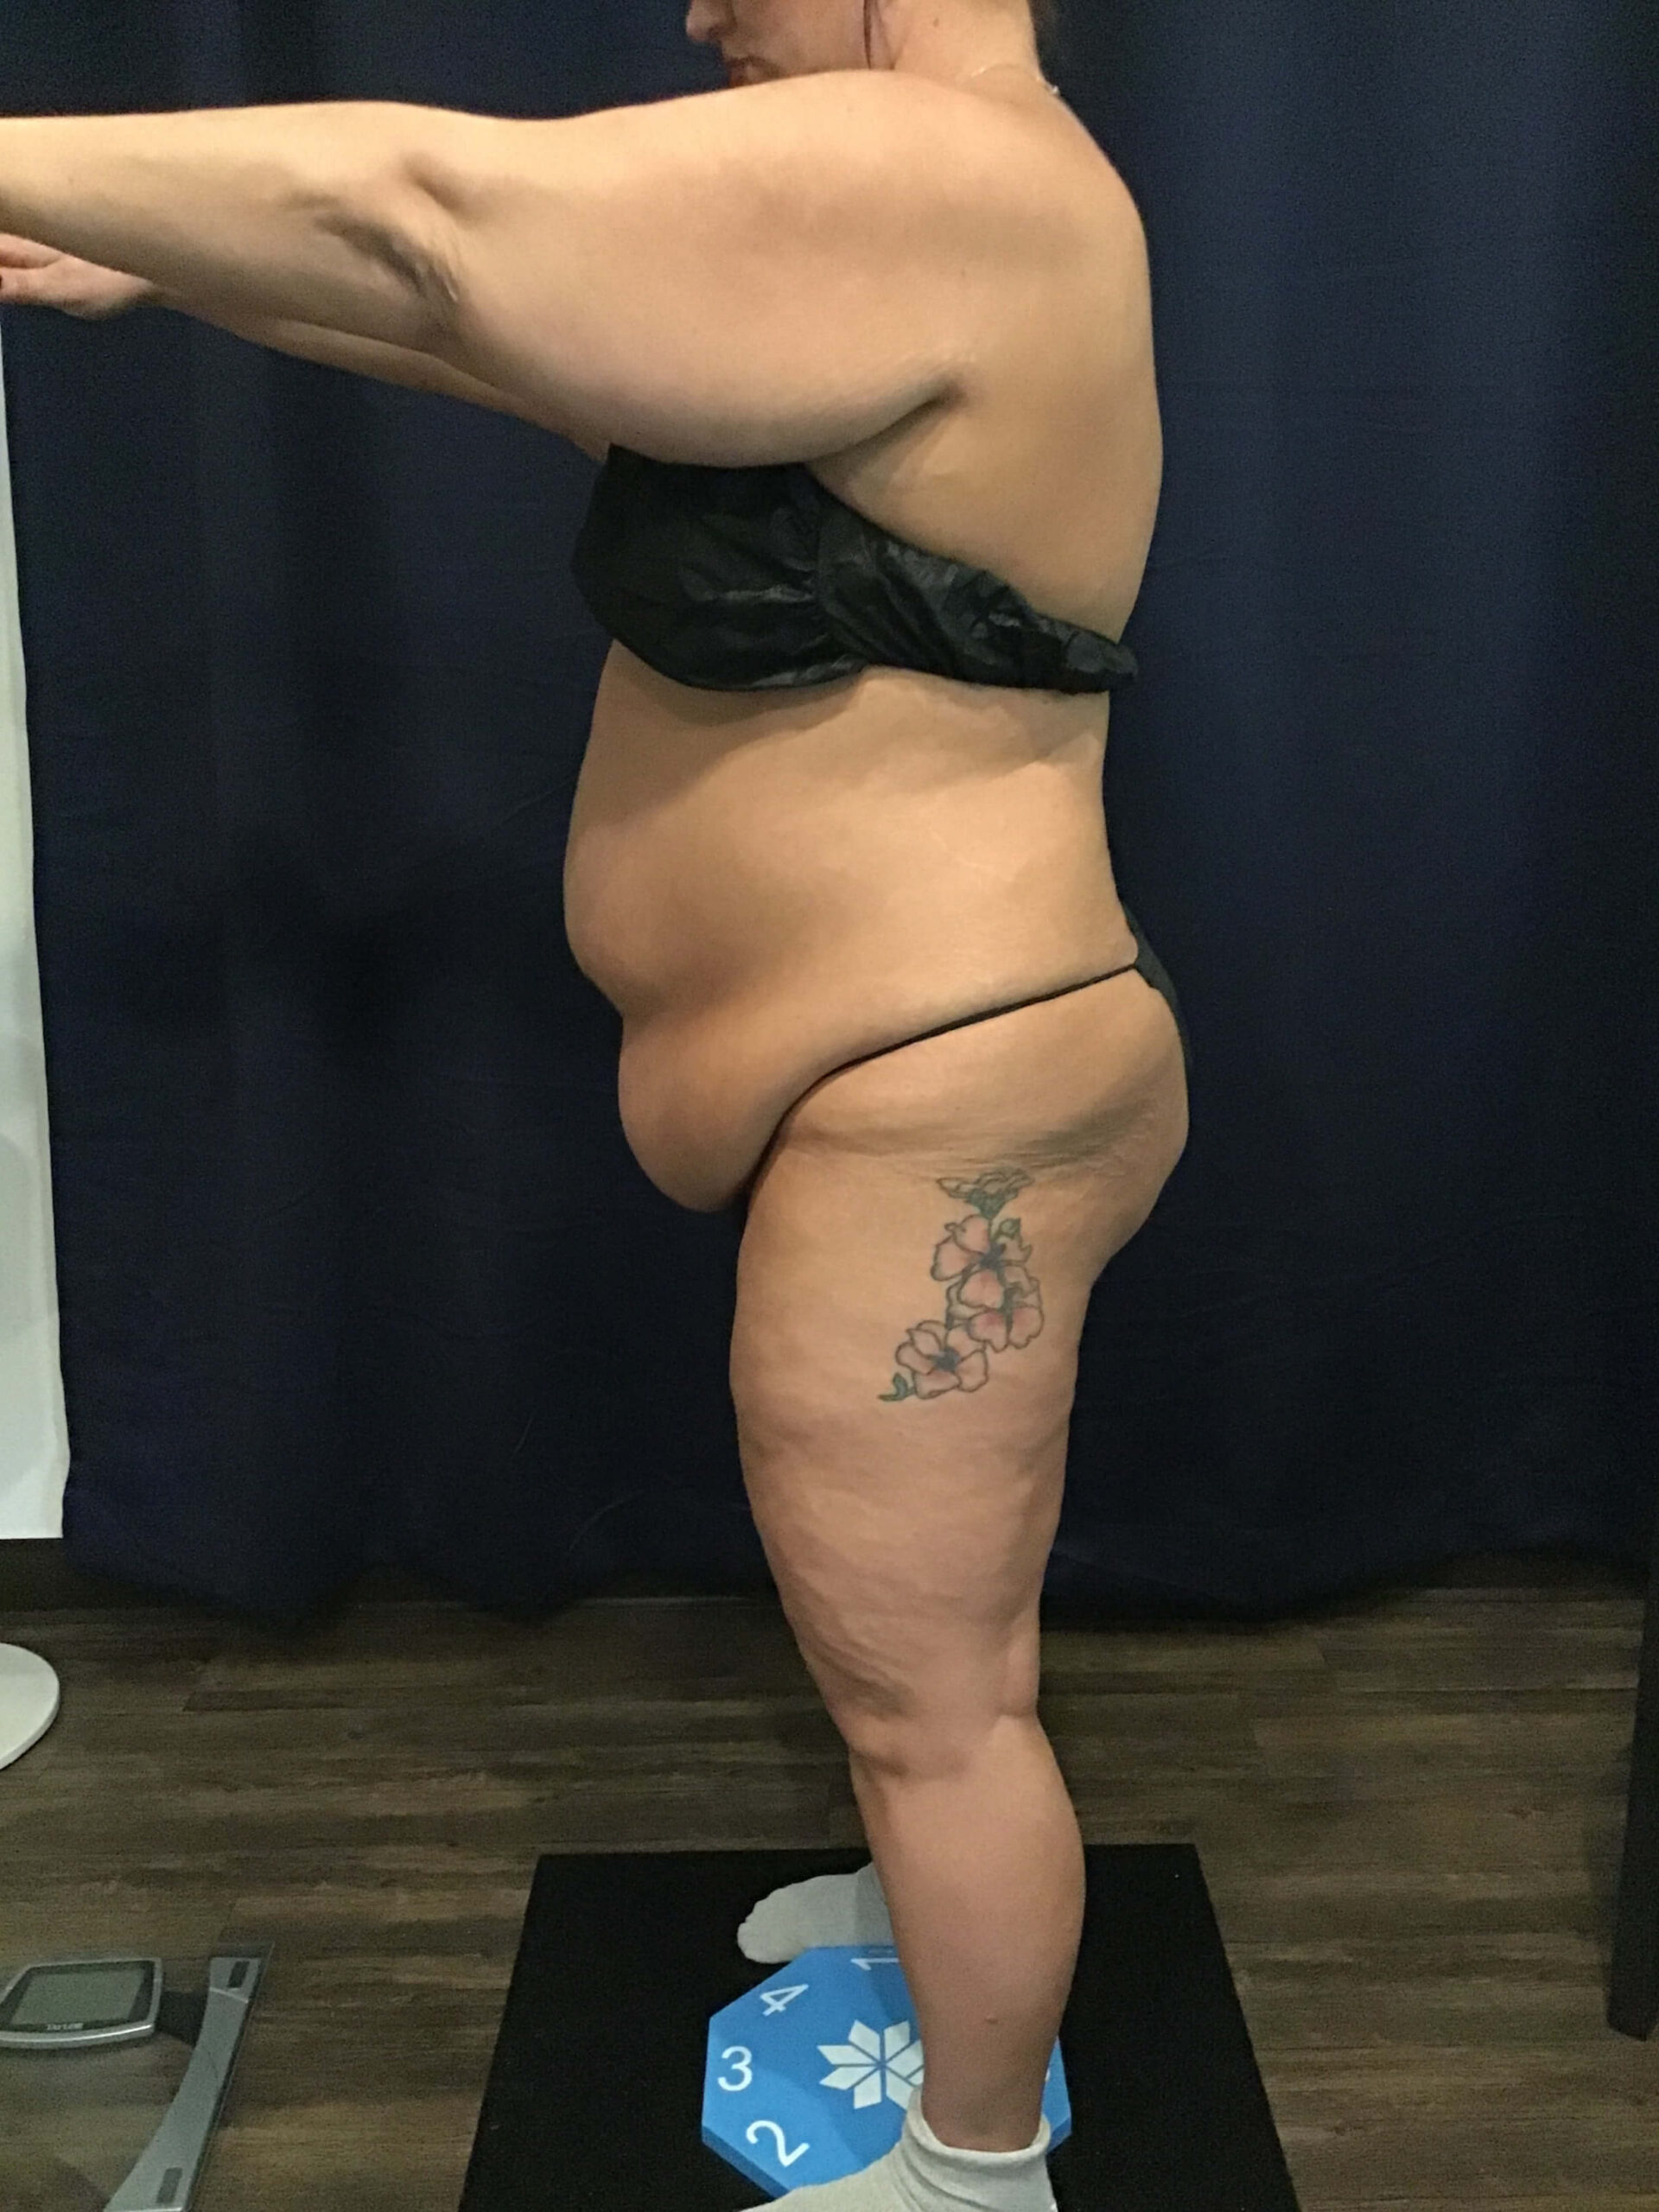
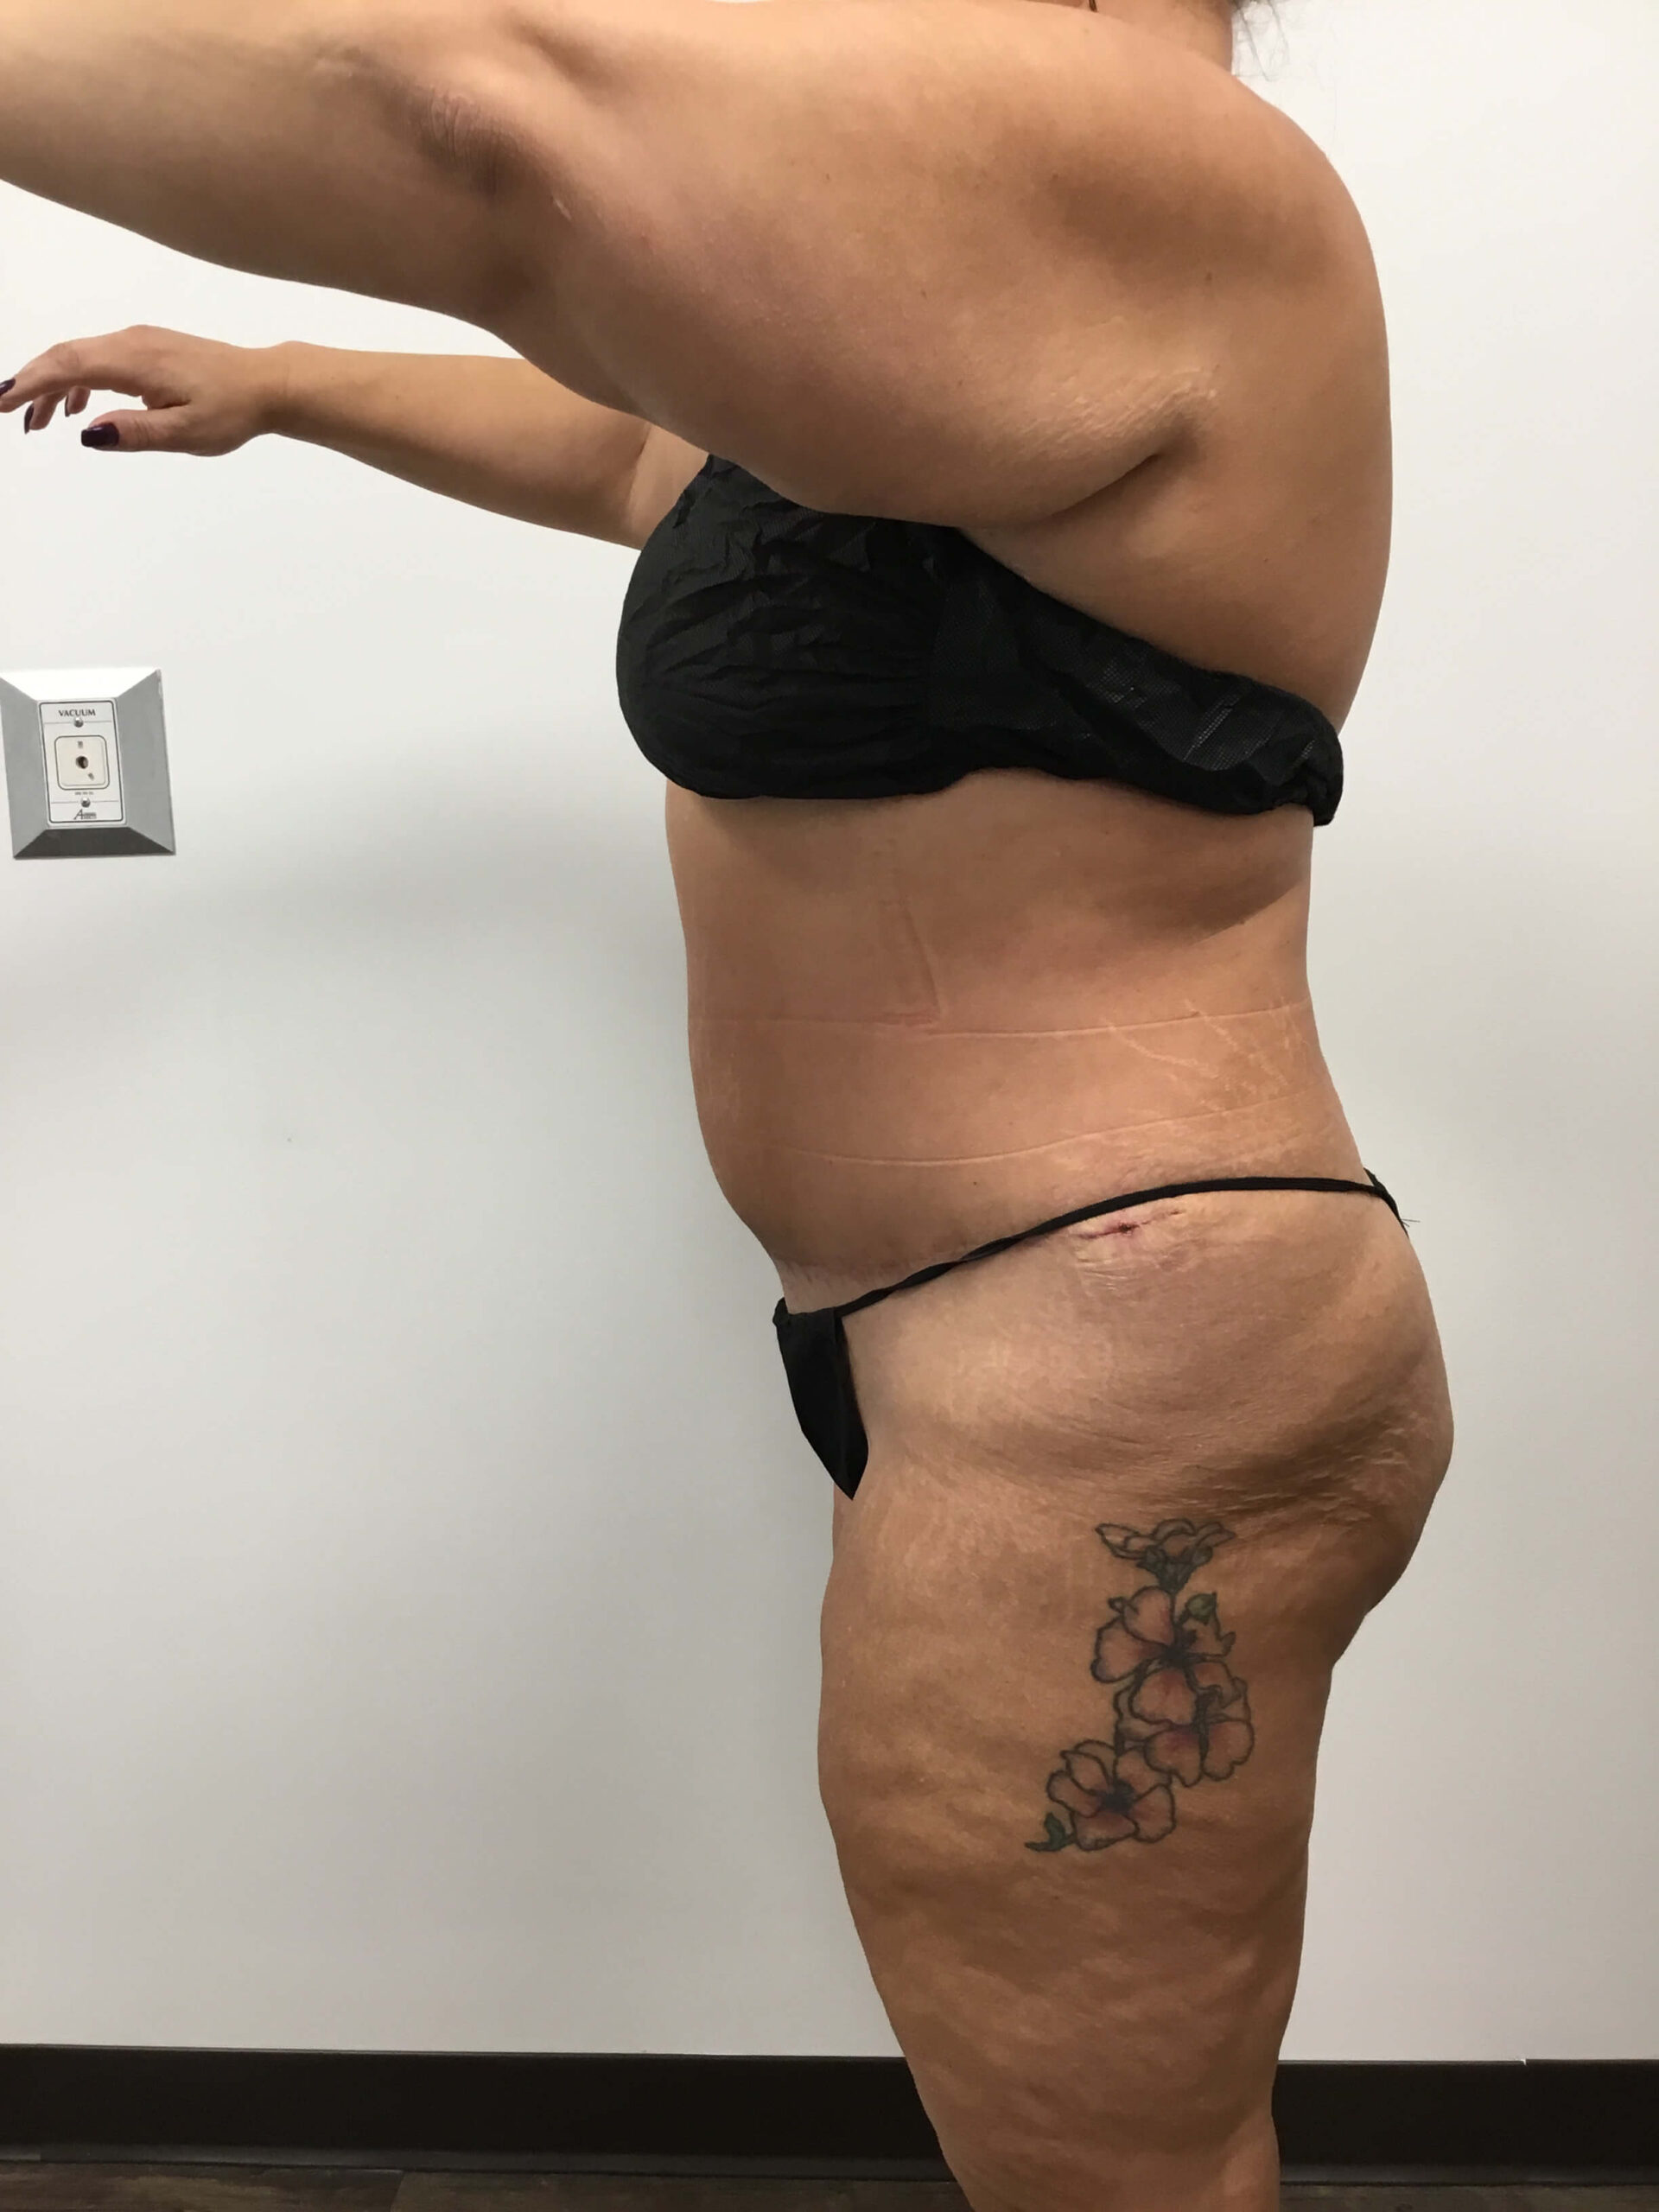
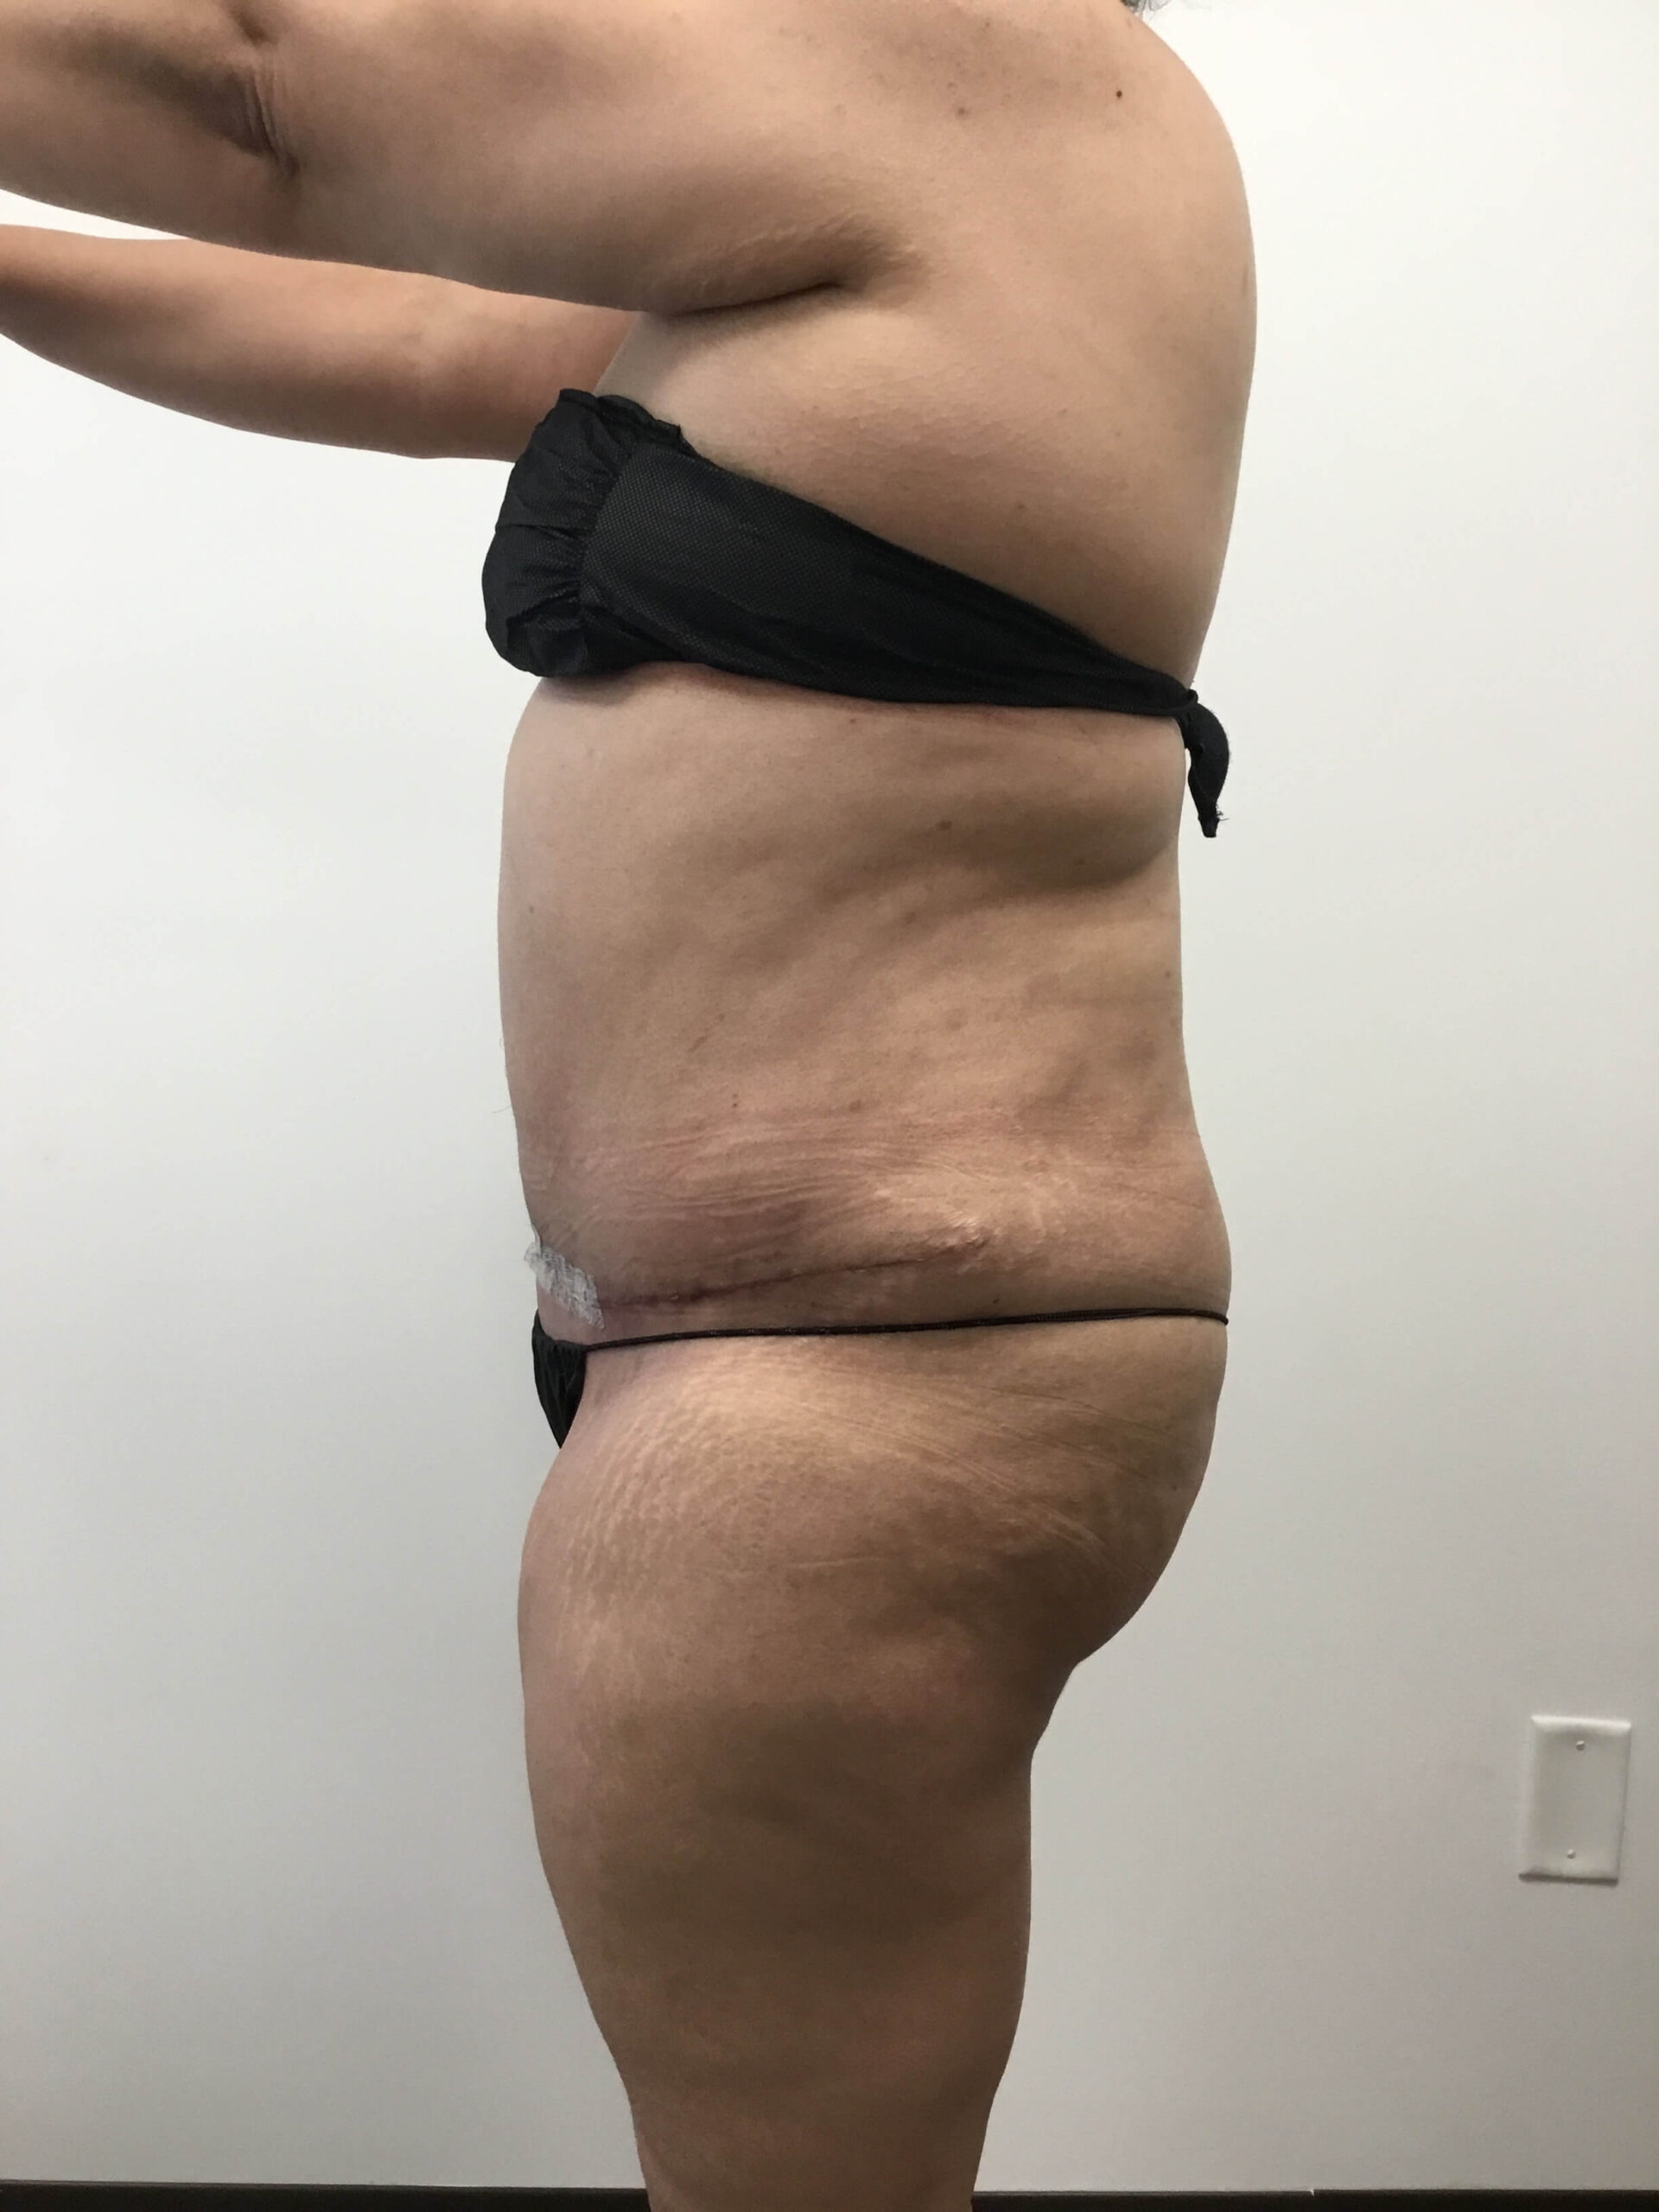
Significant loose skin and tissue - post-pregnancy, post-GLP-1, lifestyle weight loss, or post-bariatric (any volume of weight loss, including 200+ lbs). The skin no longer retracts. The pinch test reveals laxity that does not pull back into place.
TickleTuckAwake abdominoplasty · no general anesthesia · same-day home
What it does
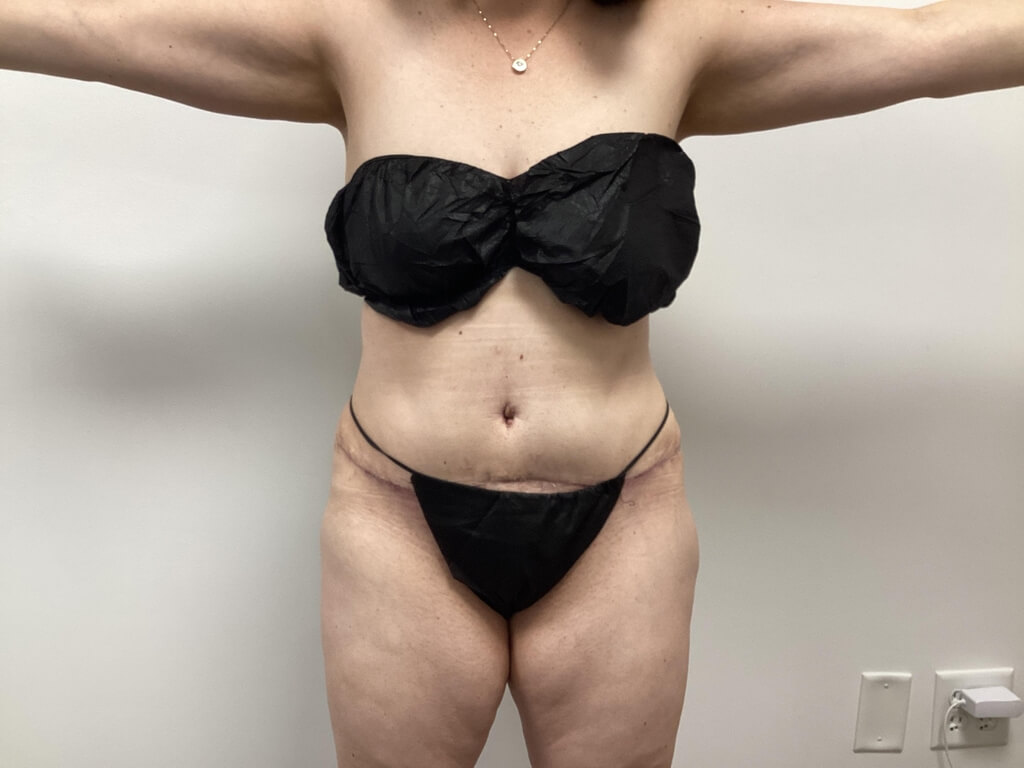
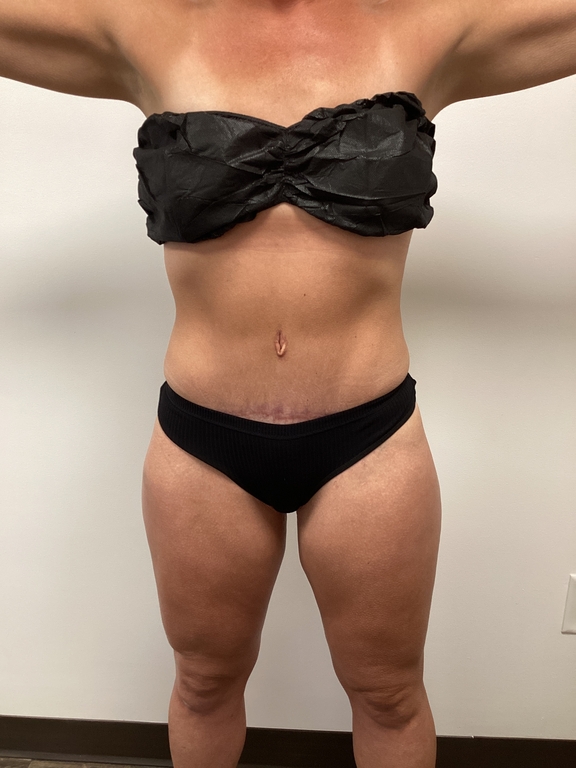
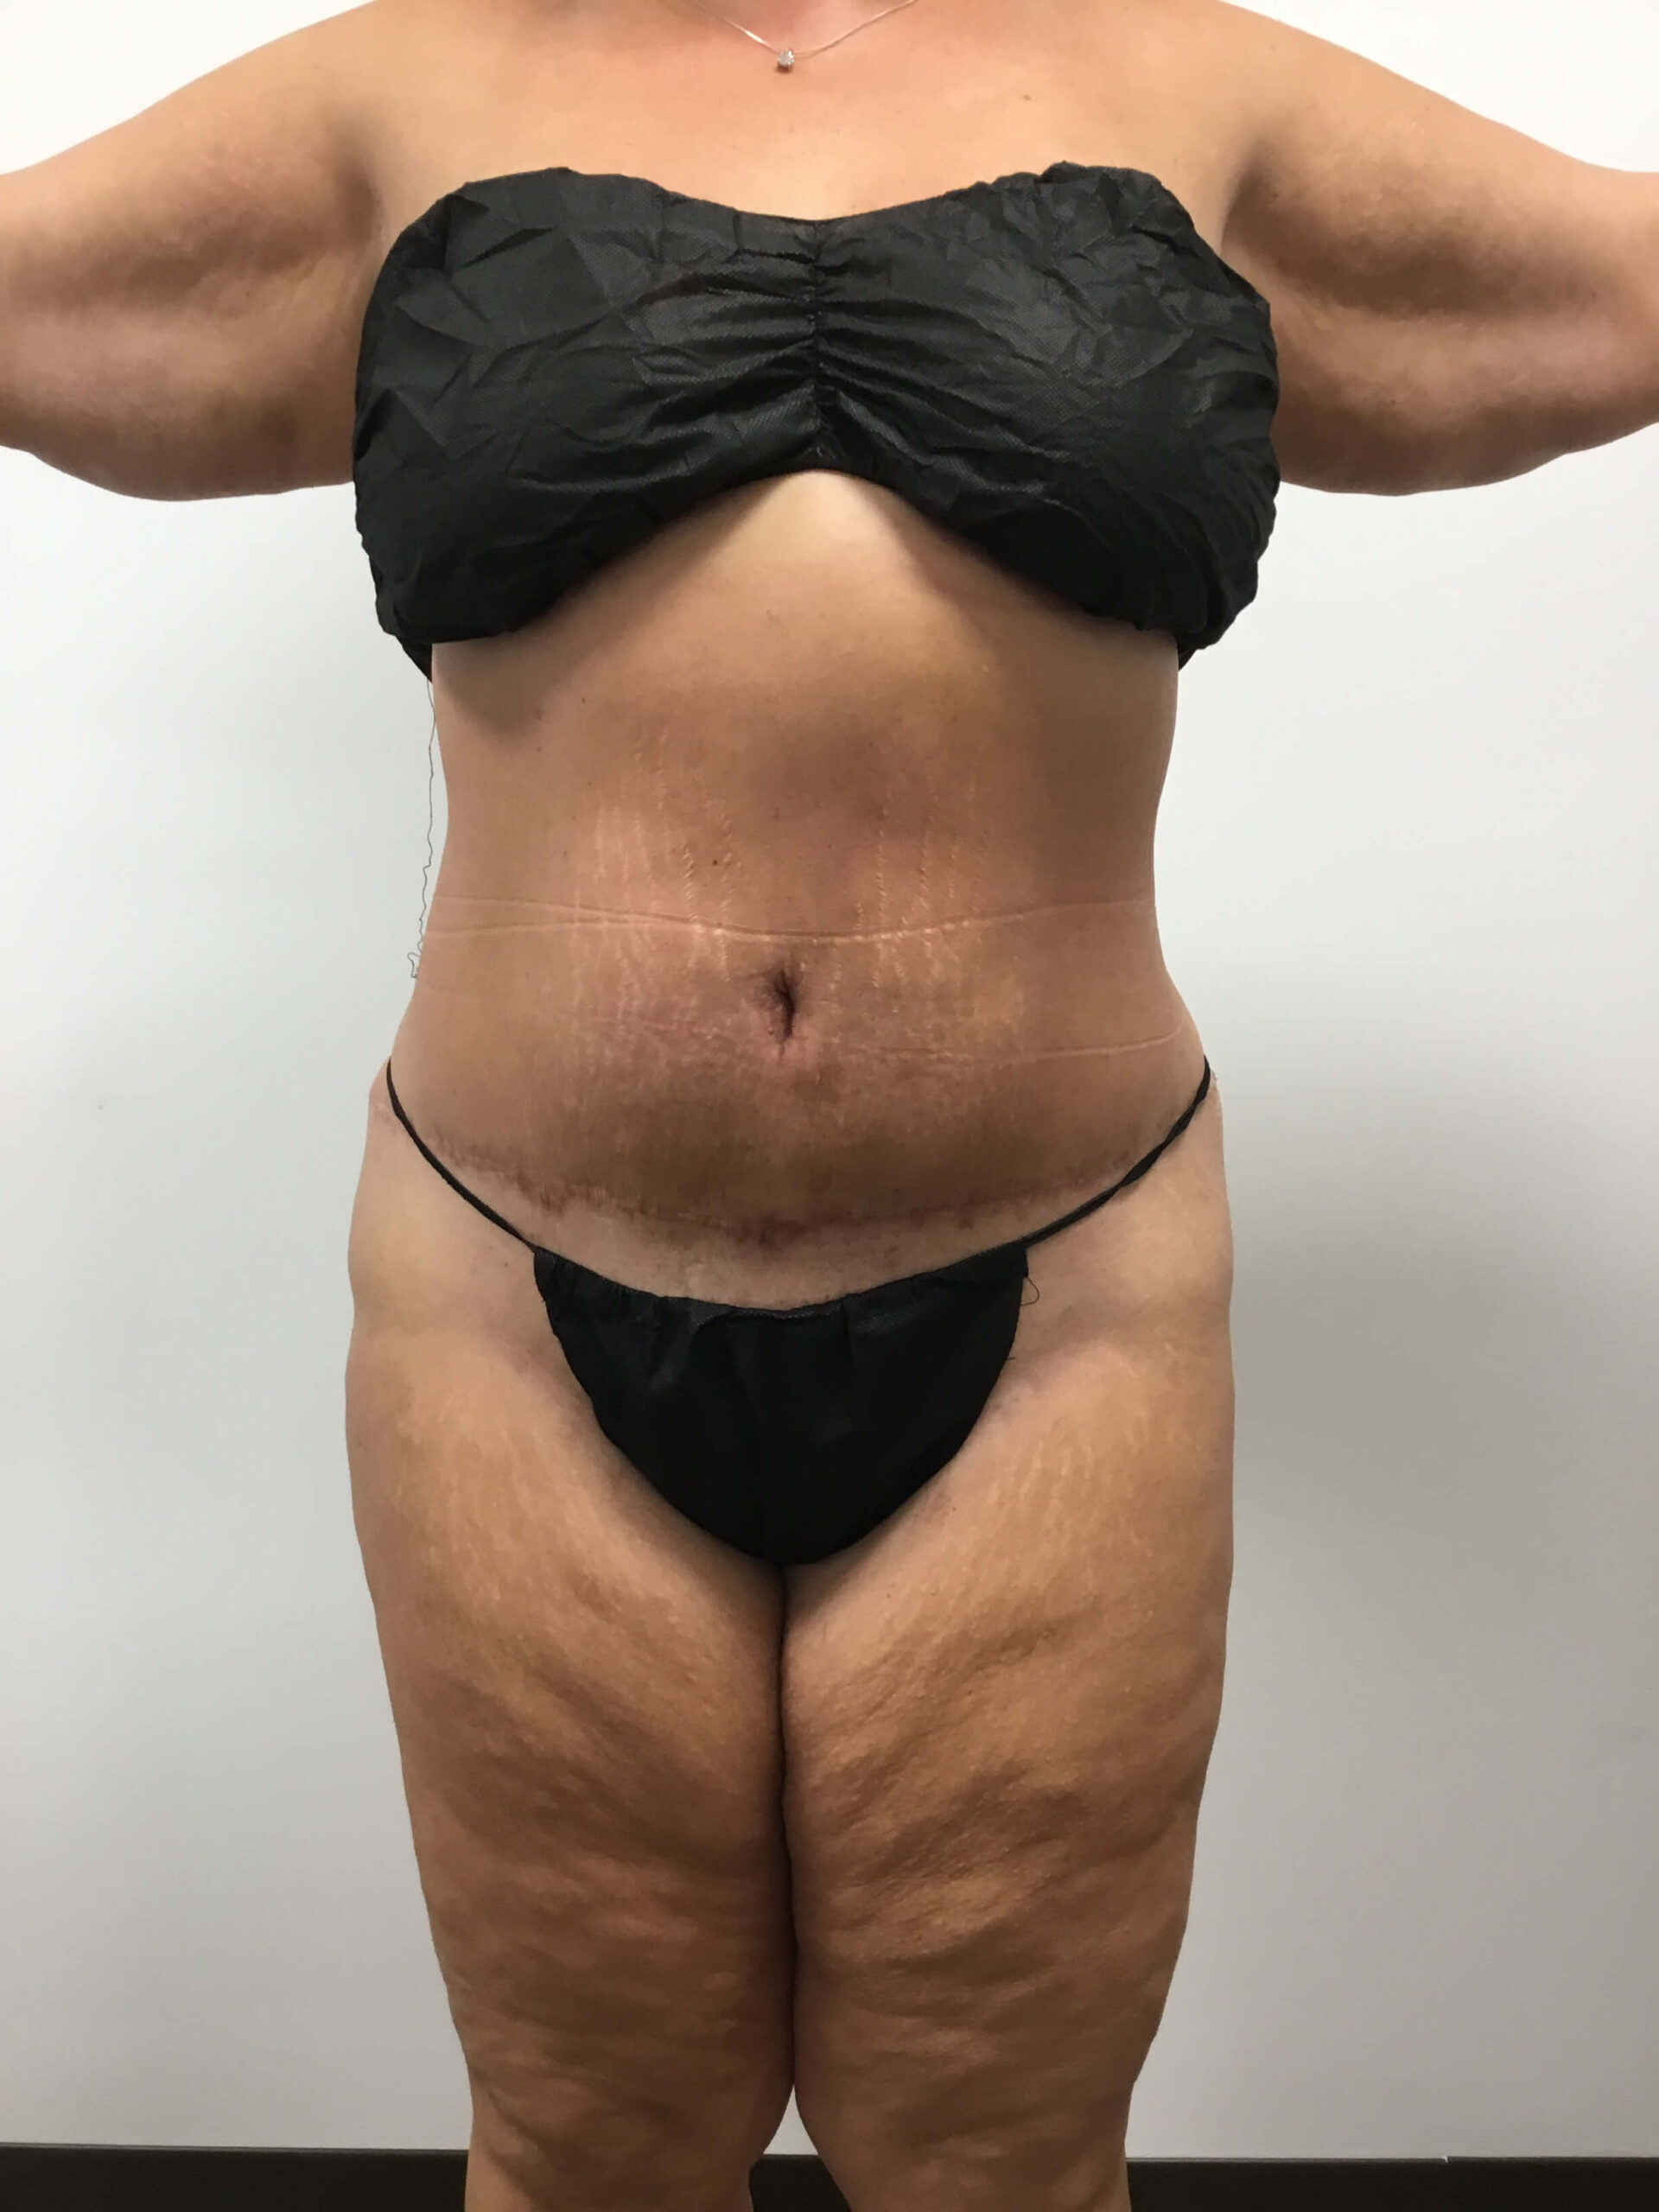
Full abdominoplasty. Excess skin removed, contour restored. Performed awake under tumescent local anesthesia, in-office, no general anesthesia, no hospital, no drains, same-day home. The largest single TickleTuck case at this practice removed 109 cm of skin in length and 40 cm in height. Why awake matters clinically, and not just for comfort, is the subject of awake versus general anesthesia.
What it won't do
Will not address visceral fat (addressed by our in-house GLP-1 program). Will not address diastasis if separation exceeds 3 cm (referred out to plastic surgeon currently, in-house with Dr. Ian Zelko 2027).
Diastasis recti separation over 3 cm.
Coordinated plicationExternal surgical colleague now · in-house 2027 with Dr. Ian Zelko
What it does
Surgical plication of the rectus fascia by an appropriate surgical colleague. Coordinated with Zelko Aesthetics for any combined skin and fat work.
What it won't do
TickleLipo or TickleTuck alone will not fix this - and TickleLipo can make the appearance worse.
04 · Self-Assessment
A three-step self-assessment, before you call.
You can perform this on yourself, right now, before any consultation. The results are not a diagnosis. They are a strong indication of which procedure is most likely to be the right one - and which ones to take off the table. If you are not yet sure contouring is even the right category, start one step earlier: the Mirror Test settles contouring versus weight loss with one question.
01
Step One
The Pinch Test
Stand in front of a mirror. Place your thumb and index finger on the area you want to change. Pinch a section of tissue between them.
If you can pinch primarily a soft, mobile fat layer that thins and disappears when you release it: subcutaneous fat is the dominant cause. Likely procedure: TickleLipo.
If you can pinch loose skin that does not snap back into place when released - skin that hangs, folds, or feels "empty": loose skin is the dominant cause. Likely procedure: TickleTite or TickleTuck.
If your abdomen is hard, distended, and there is little to pinch despite the protrusion: visceral fat is the dominant cause. No surgical procedure will address this - but our in-house GLP-1 program is built specifically for visceral fat reduction.
02
Step Two
The Skin-Pull Test
For those whose pinch test indicated loose skin. Pinch a section of loose abdominal skin, pull it firmly away from your body, and release it.
Skin pulls away one inch or less and snaps back quickly: mild laxity. TickleTite is likely sufficient.
Skin pulls away more than one inch and returns slowly: moderate-to-significant laxity. A tuck is likely indicated.
Skin remains visibly displaced after release - does not return to baseline: significant laxity. TickleTuck is the procedure matched to this - regardless of whether your weight loss was 30 lbs or 250 lbs.
03
Step Three
The Diastasis Check
For post-pregnancy guests. Lie on your back, knees bent, feet flat. Lift your head and shoulders slightly off the floor - a partial crunch. Place your fingers horizontally just above your belly button and press gently into your midline.
1-finger gap or less: no clinically significant diastasis. Plication not indicated.
2-finger gap: borderline. Individual assessment required.
3-finger gap or wider: clinically significant diastasis. Plication indicated - referred out to a plastic surgeon currently, in-house with Dr. Ian Zelko in 2027.
If you discover significant diastasis on this test, that does not disqualify you from being our guest. It means your case is referred out for the plication portion until Dr. Ian Zelko brings that capability in-house in July 2027 - and the consultation conversation is worth having now, regardless of timing.
05 · The Progression
The four-tier progression - matched to what your body actually needs.
Tier 1 · TickleLipo Alone
Mild-to-moderate fat. No meaningful skin laxity.
A single procedure: awake liposculpture, 3.5mm cannula, same-day home. This is the right answer for the guest whose skin still retracts well and whose only complaint is fat that diet and exercise have not addressed.
Tier 2 · TickleTite (TickleLipo + Renuvion)
Fat plus mild-to-moderate skin laxity. Add Secret RF for crepey skin.
Renuvion radiofrequency is added in the same session to tighten the skin envelope as fat is removed. Renuvion uses helium plasma combined with monopolar radiofrequency current placed in the subcutaneous tissue - heating the lax fibrous skin support structures so they contract over time. Full Renuvion mechanism on the TickleTite page If crepey skin is also a concern, Secret RF microneedling can be added on the Z-Spa side to enhance collagen formation and promote smoother-appearing skin. The TickleTite + Secret RF combination addresses three issues at once - fat, laxity, and skin texture.
Tier 3 · TickleTuck (TickleLipo + Tummy Tuck)
Significant loose skin. Excision required, not just tightening.
The TickleLipo portion is always performed first to create the laxity that determines exactly how much skin can and should be removed. Sequence is not flexible: lipo first, tuck second, in the same session. This is the standard for any guest with significant loose skin - post-pregnancy, lifestyle weight loss of 100+ lbs, or post-bariatric weight loss of 150–250+ lbs. The largest single case at this practice removed 109 cm of skin in length and 40 cm in height - awake, in-office, same-day home. For fullness above the navel rather than below it, there is a purpose-built variant: the reverse TickleTuck.
Tier 4 · When Significant Diastasis Is Present
Muscle plication. Referred out now. In-house with Dr. Ian Zelko in 2027.
When clinically significant diastasis (over 3 cm) is part of the picture, muscle plication is indicated. This is not currently offered in-house. Until Dr. Ian Zelko joins the practice in July 2027, plication cases are referred to a plastic surgeon - they handle the case from there. No joint care plan, no split procedure, no shared management. We refer the case out cleanly so you receive it at a setting equipped for it. That is the honest description: a referral, not a coordination. Guests with significant diastasis who would prefer the entire procedure under one roof at this practice have the option to schedule a diagnostic consultation now and be added to the priority list for July 2027 - informational only, commits you to nothing.
06 · Honest Routing
How referrals work - when we are not the right answer .
Some cases - clinically significant diastasis, certain rare presentations - are better served elsewhere. When that is true, we say so directly. Visceral fat is no longer in this category; the in-house GLP-1 program addresses it. Here is how we handle the cases we do refer out.
- Diastasis · Over 3cm
- Plication is referred to a plastic surgeon. They handle the case from there - full case, their care, their facility. We do not co-manage. The honest description: a referral, not a coordination. This changes in July 2027 when Dr. Ian Zelko joins the practice and brings plication capability in-house.
- Visceral Fat · Primary Cause · In-House Pathway
- Addressed in-house through our GLP-1 Medical Weight Loss program . Visceral fat is what GLP-1 medications were designed for - clinical trials show preferential reduction of visceral fat compared to subcutaneous fat. The same practice that manages your weight loss is the one that performs the body contouring after, when contouring is needed. No external referral required.
- Cases Outside Our Scope · Rare
- When we encounter a case better served by a board-certified plastic surgeon in a hospital setting - most often involving complications, prior surgical revisions of unusual complexity, or cases requiring general anesthesia for non-cosmetic reasons - we refer to specific surgeons we have worked with and trust. The referral is named and direct, not an internet search.
Referrals are not a soft sell. They are a clinical decision. Dr. Zelko's standard is that the guest leaves the consultation with the right answer for her body, even when the right answer is "not this practice, not yet, or not at all."
07 · The Consultation
What if you are still not sure?
That is the most common situation, and it is what consultations are for. The self-assessment above narrows the field to one or two procedures and eliminates the others. The consultation - physical examination, measurement, conversation about your goals and constraints - closes the decision.
There is no obligation. There is no procedure pressure. The standard we apply to the published clinical evidence on the rest of this site is the same standard we apply to you: precision, transparency, and the right answer for your situation, even when that answer involves another provider.
08 · Questions
What guests ask before choosing.
How do I know which procedure I need?
The procedure is matched to the cause, not chosen from a menu. Mild-to-moderate fat with no meaningful skin laxity points to TickleLipo. Fat plus mild-to-moderate skin laxity points to TickleTite. Significant loose skin that requires excision rather than tightening points to TickleTuck. Only an in-person physical examination confirms which one applies to you.
What if I have muscle separation, or diastasis recti?
Separation over 3 cm calls for surgical plication of the rectus fascia, which is coordinated with an external surgical colleague now. Dr. Ian Zelko brings plication capability in-house in 2027. Discovering significant diastasis on the self-assessment does not disqualify you from being our guest, it changes who performs that part of the work.
Is TickleTuck performed under general anesthesia?
No. TickleTuck is a full abdominoplasty performed awake under tumescent local anesthesia, in-office, with excess skin removed and contour restored. You go home the same day.
Can I decide on the procedure myself before the consultation?
The self-assessment on this page narrows the field to one or two procedures and eliminates the others. The consultation, which is a physical examination, measurement, and a conversation about your goals and constraints, closes the decision. There is no obligation and there is no procedure pressure.
What happens if body contouring is not the right answer for me?
You are told directly. Referrals are not a soft sell, they are a clinical decision. The standard is the right answer for your situation, even when that answer is not this practice, not yet, or not at all.